









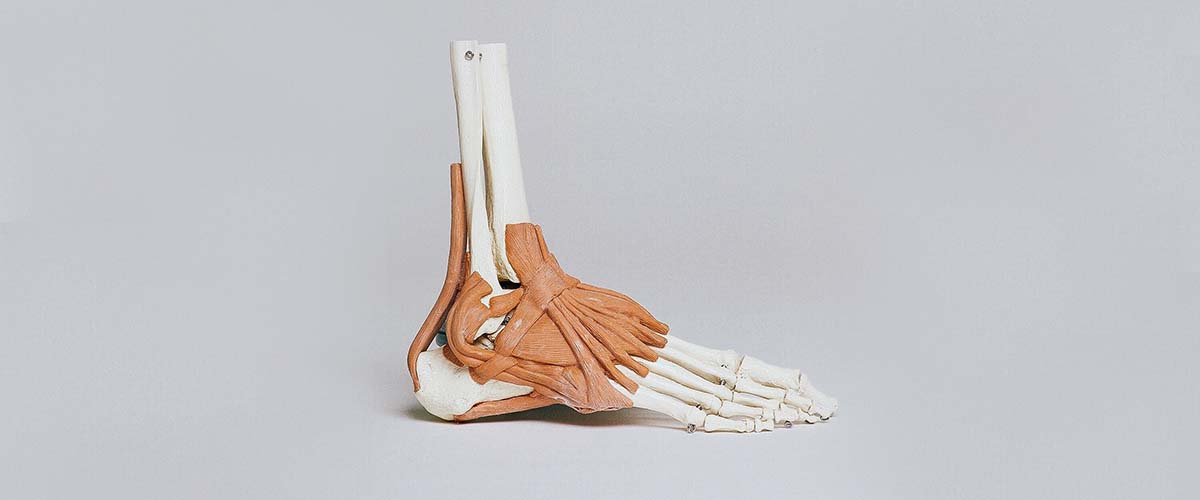
The Achilles tendon connects the calf muscles to the heel bone. It is the strongest tendon in the body, but it can rupture during explosive movements such as sprinting, jumping or pushing off, most often in recreational athletes in their thirties and forties. Most people feel a sudden “pop,” as if they were kicked in the back of the ankle, followed by pain and difficulty walking.
Acute Achilles Tendon Ruptures: An Update on Current Management Strategies
Andrew P. Dold, MD. Journal of the American Academy of Orthopaedic Surgeons (JAAOS). 2025;33(16):881–889.
In this review article, Dr. Dold brings together the research on treating a torn Achilles tendon: surgery versus non-surgical care, accelerated rehabilitation, minimally invasive repair and PRP. This page is based on that review and the 35 studies it cites.
Symptoms
- A sudden pop or snap in the back of the ankle or calf
- Sharp pain, then swelling and bruising above the heel
- Weakness pushing off, trouble walking or standing on tiptoe
- Sometimes a gap you can feel in the tendon
An Achilles rupture should be seen promptly. Early treatment matters, whether or not surgery is chosen.
Diagnosis
Dr. Dold can usually diagnose a rupture with a history and exam, including the calf-squeeze (Thompson) test. X-rays rule out a fracture. Dr. Dold will generally order an ultrasound or MRI with the ankle pointed down (plantar flexed) to measure the gap between the tendon ends. The size of that gap is one of the most important factors in predicting whether non-surgical treatment is likely to succeed.
The treatment decision also depends on patient factors (age, activity level, medical conditions) and injury factors (complete or partial tear, open or closed injury, the gap between the tendon ends).
Surgery or no surgery? What the research shows
For many years, surgery was the standard treatment because older studies showed higher re-rupture rates when the tendon was treated in a cast. That picture has changed. When non-surgical treatment uses early weight bearing and accelerated functional rehabilitation instead of long periods in a cast, research shows:
- Re-rupture rates similar to surgical repair
- Comparable strength, motion and return to activity for most patients
- No risk of surgical complications such as wound infection, scar adhesion or injury to the sural nerve
A landmark randomized trial by Willits and colleagues at Western University in Canada (Journal of Bone and Joint Surgery, 2010) was among the first to show this. Dr. Dold’s 2025 review in the Journal of the American Academy of Orthopaedic Surgeons brings together the research since then (see below).
Non-surgical treatment: Dr. Dold’s accelerated rehabilitation program
Non-surgical treatment is not “doing nothing.” It is a structured, closely supervised program. In general:
- First 2 weeks: a walking boot with heel lifts keeps the foot pointed down so the tendon ends stay together. You use crutches and don’t put weight on the leg.
- From about 2 weeks: physical therapy begins, with protected weight bearing in the boot.
- From about 4 weeks: weight bearing as tolerated in the boot, with the heel lifts gradually lowered.
- About 8 to 12 weeks: you wean out of the boot into a regular shoe.
- After 12 weeks: strength, power and sport-specific training.
Your plan is tailored to you, and Dr. Dold and your therapist follow your progress closely, including watching for blood clots.
When surgery may be recommended
Surgery remains a good option for some patients, such as certain high-level athletes and patients who prefer surgery after discussing the options with Dr. Dold. There are a variety of surgical options to consider, from minimally invasive (percutaneous and mini-open) techniques to a traditional open repair. Dr. Dold will recommend the right option for you based on your goals and the patient and injury factors described above. The same accelerated rehabilitation principles are used after surgery.
Watch Dr. Dold explain Achilles tendon ruptures
Recovery and return to sport
With either treatment, most patients are walking in a regular shoe by about 3 months. Return to running usually takes about 4 to 5 months, and return to sport about 6 to 9 months, depending on strength testing and the demands of your sport.
Dr. Dold’s research on Achilles ruptures
Dold AP. Acute Achilles Tendon Ruptures: An Update on Current Management Strategies. Journal of the American Academy of Orthopaedic Surgeons. 2025;33(16):881–889. Read the article (doi:10.5435/JAAOS-D-24-00275)
In this review, Dr. Dold examined the research comparing surgical and non-surgical treatment. Key findings, in plain language:
- With early weight bearing and accelerated rehabilitation, non-surgical treatment has re-rupture rates comparable to surgery.
- Surgery carries risks that non-surgical care avoids, including infection, scar adhesion and sural nerve injury.
- Newer minimally invasive surgical techniques reduce some surgical complications compared with traditional open repair.
- Evidence for adding orthobiologics such as platelet-rich plasma (PRP) is mixed. Dr. Dold can discuss whether they have a role in your treatment.
- There is no single right treatment for everyone. Patients should understand the benefits and risks of each option and choose the plan that fits their goals.
All 35 studies cited in the review are listed, with PubMed links, under Research cited on this page at the bottom of this page.
You can also read “I tore my Achilles tendon. Do I need surgery?” on our blog.
Why see Dr. Dold
- Author of Acute Achilles Tendon Ruptures: An Update on Current Management Strategies, Journal of the American Academy of Orthopaedic Surgeons (JAAOS), 2025
- Board certified by the American Board of Orthopaedic Surgery, with subspecialty certification in Sports Medicine
- Fellow of the American Orthopaedic Association (FAOA), the American Academy of Orthopaedic Surgeons (FAAOS), the American College of Surgeons (FACS) and the Royal College of Surgeons of Canada (FRCSC)
- Sports medicine and arthroscopy fellowship at NYU Langone / Hospital for Joint Diseases; orthopedic residency at the University of Toronto
- D Magazine Best Doctors (Collin County), 2019–2026 · Rated 4.9 on Google
Frequently asked questions
Do I need surgery for a torn Achilles tendon?
Not necessarily. For most acute ruptures, non-surgical treatment with early weight bearing and accelerated rehabilitation is a proven option with re-rupture rates similar to surgery. Some patients are better served by surgery, and Dr. Dold will go over the options with you.
Is non-surgical treatment of an Achilles rupture as good as surgery?
Research using modern accelerated rehabilitation protocols shows comparable re-rupture rates and similar function for most patients, without surgical risks such as infection or nerve injury.
How long will I be in a boot after an Achilles rupture?
Typically about 8 to 12 weeks, starting with heel lifts and crutches, then gradually increasing weight bearing before weaning into a regular shoe.
How long does it take to recover from an Achilles rupture?
Most patients are walking in a regular shoe by about 3 months. Return to running usually takes about 4 to 5 months, and return to sport about 6 to 9 months, depending on strength testing.
How soon should I see a doctor after an Achilles rupture?
As soon as possible, ideally within the first few days. Starting treatment early is important whether or not you have surgery.
Research cited on this page
These are the 35 studies cited in Dr. Dold’s review, listed in the order they appear in the article.
Dold AP. Acute Achilles Tendon Ruptures: An Update on Current Management Strategies. J Am Acad Orthop Surg. 2025;33(16):881–889. doi:10.5435/JAAOS-D-24-00275 · PubMed
- Alcelik I, Saeed ZM, Haughton BA, et al.: Achillon versus open surgery in acute Achilles tendon repair. Foot Ankle Surg 2018;24:427-434. PubMed
- Myhrvold SB, Brouwer EF, Andresen TKM, et al.: Nonoperative or surgical treatment of acute achilles’ tendon rupture. N Engl J Med 2022;386:1409-1420. PubMed
- She G, Teng Q, Li J, Zheng X, Chen L, Hou H: Comparing surgical and conservative treatment on achilles tendon rupture: A comprehensive metaanalysis of RCTs. Front Surg 2021;8:607743. PubMed
- Deng S, Sun Z, Zhang C, Chen G, Li J: Surgical treatment versus conservative management for acute achilles tendon rupture: A systematic review and meta-analysis of randomized controlled trials. J Foot Ankle Surg 2017;56:1236-1243. PubMed
- Ecker TM, Bremer AK, Krause FG, Müller T, Weber M: Prospective use of a standardized nonoperative early weightbearing protocol for achilles tendon rupture: 17 years of experience. Am J Sports Med 2016;44:1004-1010. PubMed
- Ochen Y, Beks RB, van Heijl M, et al.: Operative treatment versus nonoperative treatment of achilles tendon ruptures: Systematic review and meta-analysis. BMJ 2019;364:k5120. PubMed
- Park SH, Lee HS, Young KW, Seo SG: Treatment of acute achilles tendon rupture. Clin Orthop Surg 2020;12:1-8. PubMed
- Soroceanu A, Sidhwa F, Aarabi S, Kaufman A, Glazebrook M: Surgical versus nonsurgical treatment of acute achilles tendon rupture: A metaanalysis of randomized trials. J Bone Joint Surg Am 2012;94:2136-2143. PubMed
- Jamjoom BA: The influence of early weightbearing, controlled motion, and timing of orthosis removal on the nonoperative management of achilles tendon rupture: A systematic review. J Foot Ankle Surg 2021;60:777-786. PubMed
- Möller M, Movin T, Granhed H, Lind K, Faxén E, Karlsson J: Acute rupture of tendon Achillis. A prospective randomised study of comparison between surgical and non-surgical treatment. J Bone Joint Surg Br 2001;83:843-848. PubMed
- Twaddle BC, Poon P: Early motion for achilles tendon ruptures: Is surgery important?: A randomized, prospective study. Am J Sports Med 2007;35:2033-2038. PubMed
- Lim CS, Lees D, Gwynne-Jones DP: Functional outcome of acute achilles tendon rupture with and without operative treatment using identical functional bracing protocol. Foot Ankle Int 2017;38:1331-1336. PubMed
- Dai W, Leng X, Wang J, Hu X, Ao Y: Rehabilitation regimen for nonsurgical treatment of achilles tendon rupture: A systematic review and metaanalysis of randomised controlled trials. J Sci Med Sport 2021;24:536-543. PubMed
- Mark-Christensen T, Troelsen A, Kallemose T, Barfod KW: Functional rehabilitation of patients with acute achilles tendon rupture: A metaanalysis of current evidence. Knee Surg Sports Traumatol Arthrosc 2016;24:1852-1859. PubMed
- Heikkinen J, Lantto I, Flinkkila T, et al.: Soleus atrophy is common after the nonsurgical treatment of acute achilles tendon ruptures: A randomized clinical trial comparing surgical and nonsurgical functional treatments. Am J Sports Med 2017;45:1395-1404. PubMed
- Wang C, Fan H, Li Y, Yun Z, Zhang Z, Zhu Q: Effectiveness of platelet-rich plasma injections for the treatment of acute achilles tendon rupture: A systematic review and meta-analysis. Medicine (Baltimore) 2021;100:e27526. PubMed
- Keene DJ, Alsousou J, Harrison P, et al.: Platelet-rich plasma injection for acute achilles tendon rupture: Two-year follow-up of the PATH-2 randomized, placebo-controlled, superiority trial. Bone Joint J 2022;104B:1256-1265. PubMed
- Zou J, Mo X, Shi Z, et al.: A prospective study of platelet-rich plasma as biological augmentation for acute achilles tendon rupture repair. Biomed Res Int 2016;2016:9364170. PubMed
- Boksh K, Elbashir M, Thomas O, Divall P, Mangwani J: Platelet-rich plasma in acute achilles tendon ruptures: A systematic review and metaanalysis. Foot (Edinb) 2022;53:101923. PubMed
- Nordenholm A, Nilsson N, Senorski EH, Helander KN, Westin O, Olsson N: Patients with chronic Achilles tendon rupture have persistent limitations in patient-reported function and calf muscle function one year after surgical treatment – a case series. J Exp Orthop 2022;9:15. PubMed
- Chen H, Ji X, Zhang Q, Liang X, Tang P: Channel-assisted minimally invasive repair of acute Achilles tendon rupture. J Orthop Surg Res 2015;10:167. PubMed
- Martin KD, Crouser NJ, Khan IA: Minimally invasive mid-substance achilles tendon repair using the percutaneous achilles repair system (PARS). Essent Surg Tech 2022;12:e21.00050. PubMed
- Aktas S, Kocaoglu B: Open versus minimal invasive repair with Achillon device. Foot Ankle Int 2009;30:391-397. PubMed
- Hsu AR, Jones CP, Cohen BE, Davis WH, Ellington JK, Anderson RB: Clinical outcomes and complications of percutaneous achilles repair system versus open technique for acute achilles tendon ruptures. Foot Ankle Int 2015;36:1279-1286. PubMed
- Clanton TO, Haytmanek CT, Williams BT, et al.: A biomechanical comparison of an open repair and 3 minimally invasive percutaneous achilles tendon repair techniques during a simulated, progressive rehabilitation protocol. Am J Sports Med 2015;43:1957-1964. PubMed
- Heitman DE, Ng K, Crivello KM, Gallina J: Biomechanical comparison of the Achillon tendon repair system and the Krackow locking loop technique. Foot Ankle Int 2011;32:879-887. PubMed
- Sadoghi P, Rosso C, Valderrabano V, Leithner A, Vavken P: Initial Achilles tendon repair strength—synthesized biomechanical data from 196 cadaver repairs. Int Orthop 2012;36:1947-1951. PubMed
- Attia AK, Mahmoud K, d’Hooghe P, Bariteau J, Labib SA, Myerson MS: Outcomes and complications of open versus minimally invasive repair of acute achilles tendon ruptures: A systematic review and metaanalysis of randomized controlled trials. Am J Sports Med 2023;51:825-836. PubMed
- Jack RA, Sochacki KR, Gardner SS, et al.: Performance and return to sport after achilles tendon repair in national football league players. Foot Ankle Int 2017;38:1092-1099. PubMed
- Del Buono A, Volpin A, Maffulli N: Minimally invasive versus open surgery for acute achilles tendon rupture: A systematic review. Br Med Bull 2014;109:45-54. PubMed
- Bartel AFP, Elliott AD, Roukis TS: Incidence of complications after Achillon® mini-open suture system for repair of acute midsubstance achilles tendon ruptures: A systematic review. J Foot Ankle Surg 2014;53:744-746. PubMed
- Ismail M, Karim A, Shulman R, Amis A, Calder J: The Achillon® achilles tendon repair: Is it strong enough? Foot Ankle Int 2008;29:808-813. PubMed
- Joannas G, Arrondo G, Eslava S, et al.: Percutaneous Achilles tendon repair with the Dresden instrument. Clinical and MRI evaluation of 90 patients. Foot Ankle Surg 2020;26:209-217. PubMed
- Manegold S, Tsitsilonis S, Schumann J, et al.: Functional outcome and complication rate after percutaneous suture of fresh Achilles tendon ruptures with the Dresden instrument. J Orthop Traumatol 2018;19:19. PubMed
- Amlang MH, Christiani P, Heinz P, Zwipp H: The percutaneous suture of the Achilles tendon with the Dresden instrument. Oper Orthop Traumatol 2006;18:287-299. PubMed
Additional studies on Achilles rupture treatment (33)
- Operative versus nonoperative treatment of acute Achilles tendon ruptures: a multicenter randomized trial using accelerated functional rehabilitation
- A Prospective Randomized Trial Comparing Surgical and Nonsurgical Treatments of Acute Achilles Tendon Ruptures.
- Early functional treatment versus cast immobilization in tension after achilles rupture repair: results of a prospective randomized trial with 10 or more years of follow-up.
- Tendon Length, Calf Muscle Atrophy, and Strength Deficit After Acute Achilles Tendon Rupture: Long-Term Follow-up of Patients in a Previous Study.
- Augmented Compared with Nonaugmented Surgical Repair After Total Achilles Rupture: Results of a Prospective Randomized Trial with Thirteen or More Years of Follow-up
- Accelerated rehabilitation following Achilles tendon repair after acute rupture – Development of an evidence-based treatment protocol.
- Cost-effectiveness analysis of surgical versus non-surgical management of acute Achilles tendon ruptures
- Practice patterns in the care of acute Achilles tendon ruptures : is there an association with level I evidence?
- Patients with an Achilles tendon re-rupture have long-term functional deficits in function and worse patient-reported outcome than primary ruptures
- Stable surgical repair with accelerated rehabilitation versus nonsurgical treatment for acute Achilles tendon ruptures: a randomized controlled study
- Predictors of functional outcome in non-operatively managed Achilles tendon ruptures.
- Outcome after operative treatment for chronic versus acute Achilles tendon rupture – A comparative analysis.
- Operative versus nonoperative management of acute Achilles tendon ruptures: a quantitative systematic review of randomized controlled trials.
- Outcomes of open surgery versus nonoperative management of acute achilles tendon rupture.
- Risk Factors for Failed Nonoperative Treatment and Rerupture in Acute Achilles Tendon Rupture
- Platelet rich Plasma in Achilles Tendon Healing 2 (PATH-2) trial: protocol for a multicentre, participant and assessor-blinded, parallel-group randomised clinical trial comparing platelet-rich plasma (PRP) injection versus placebo injection for Achilles tendon rupture.
- Rehabilitation regimen after surgical treatment of acute Achilles tendon ruptures: a systematic review with meta-analysis
- Is Operative Treatment of Achilles Tendon Ruptures Superior to Nonoperative Treatment?: A Systematic Review of Overlapping Meta-analyses.
- Effect of Early Versus Late Weightbearing in Conservatively Treated Acute Achilles TendonRupture: A Meta-Analysis.
- The Effect of Obesity on Surgical Treatment of Achilles Tendon Ruptures.
- Achilles tendon rupture healing is enhanced by intermittent pneumatic compression upregulating collagen type I synthesis.
- Professional Athletes’ Return to Play and Performance After Operative Repair of an Achilles Tendon Rupture.
- Cost-minimization Analysis of the Management of Acute Achilles Tendon Rupture.
- Severe Functional Debilitations After Complications Associated With Acute Achilles Tendon Rupture With 9 Years of Follow-Up.
- Elevated Knee Joint Kinetics and Reduced Ankle Kinetics Are Present During Jogging and Hopping After Achilles Tendon Ruptures.
- Outcome following use of the Achillon jig for the repair of acutely ruptured Achilles tendons
- Functional outcomes of conservatively managed acute ruptures of the Achilles tendon.
- The epidemiology and trends in management of acute Achilles tendon ruptures in Ontario, Canada: a population-based study of 27,607 patients
- Ageing, deep vein thrombosis and male gender predict poor outcome after acute Achilles tendon rupture.
- Is surgical intervention more effective than non-surgical treatment for acute Achilles tendonrupture? A systematic review of overlapping meta-analyses.
- Surgical Versus Conservative Intervention for Acute Achilles Tendon Rupture: A PRISMA-Compliant Systematic Review of Overlapping Meta-Analyses.
- Twelve-month outcomes following surgical repair of the Achilles tendon.
- Operative and Nonoperative Management of Achilles Tendon Ruptures in Active Duty Military Population
Medically reviewed by Andrew P. Dold, MD, FAOA, FAAOS, FACS, FRCSC. Last reviewed October 2026. This page is general information, not medical advice.


