









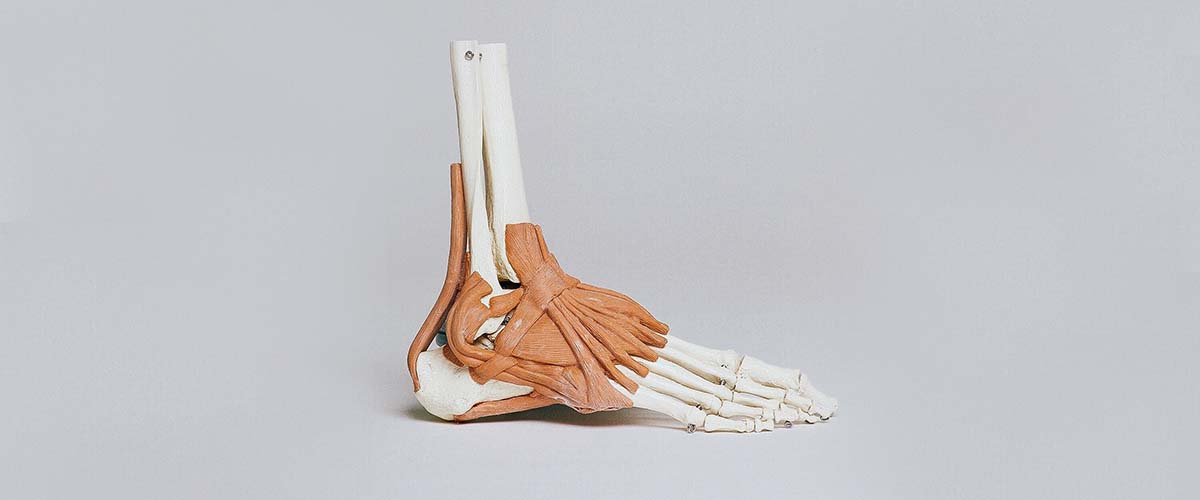
Turf toe is a sprain of the big-toe joint, called the first metatarsophalangeal (MTP) joint, where the big toe meets the foot. It happens when the big toe is forcefully bent upward while the heel is off the ground, stretching or tearing the plantar plate, the tough band of ligament and capsule on the underside of the joint. Turf toe is most common in football, but it also occurs in soccer, basketball, rugby, dance and gymnastics. Dr. Andrew Dold, a board-certified, fellowship-trained sports medicine surgeon in Frisco, Texas, evaluates and treats turf toe, from mild sprains to complete plantar plate tears.
- Turf toe is a sprain of the ligaments and plantar plate under the big-toe joint, caused by forced upward bending of the toe
- Injuries are graded I (stretch), II (partial tear) and III (complete tear)
- Most turf toe injuries are treated without surgery, with protection, a stiff-soled shoe or boot and physical therapy
- Severe (grade III) injuries can take several months to recover from, and some need surgical repair
- Pushing off is what the big toe does in sport, so getting it properly diagnosed matters
What is turf toe and how does it happen?
The big-toe joint carries a large share of your body weight when you push off to run, jump or cut. On its underside sit the plantar plate, the joint capsule, the collateral ligaments and two small bones inside the tendon called the sesamoids. Together these structures stop the toe from bending too far upward.
Turf toe occurs from a forceful hyperextension (upward bending) of the big toe.1 A classic example is a football player whose forefoot is planted on the ground with the heel raised when another player lands on the back of his leg, driving the toe upward. The name comes from the link with artificial playing surfaces and flexible shoes, which let the toe bend further than it should.
In a study of 5 seasons of college football from the NCAA Injury Surveillance System, turf toe occurred at a rate of about 0.062 injuries per 1,000 athlete-exposures. Players were nearly 14 times more likely to be injured in games than in practice, and the rate was higher on artificial turf (0.087 per 1,000) than on natural grass (0.047 per 1,000).2 Running backs and quarterbacks were most often affected, and fewer than 2% of the injuries were treated with surgery.2
Turf toe grades
| Grade | What is injured | Typical findings |
|---|---|---|
| Grade I | Stretching of the plantar plate and capsule | Mild pain and swelling; you can usually walk and the joint is stable |
| Grade II | Partial tear of the plantar plate and capsule | More pain, swelling and bruising, limited motion and pain with walking |
| Grade III | Complete tear of the plantar plate and capsule | Severe pain, swelling and bruising, difficulty bearing weight; the joint may be unstable and the sesamoids may be pulled out of place |
This grading system helps guide treatment and return to sport.1
Symptoms
- Pain at the base of the big toe, especially when pushing off
- Swelling and bruising around the joint and on the bottom of the foot
- Stiffness and loss of upward motion of the big toe
- Difficulty running, jumping or walking normally
- In severe injuries, a feeling that the toe is loose, or a toe that starts to drift or cock upward
Diagnosis
Dr. Dold will ask how the injury happened and examine the toe for tenderness, swelling, range of motion and joint stability, comparing it with the other foot. X-rays look for a fracture, a small piece of bone pulled off with the ligament, or sesamoids that have moved toward the heel, which can signal a complete plantar plate tear. Standing X-rays of both feet are often used for comparison. An MRI shows the plantar plate, capsule, cartilage and sesamoids in detail and is helpful when a grade II or III injury is suspected or the toe is not improving as expected.
Non-surgical treatment
Most turf toe injuries are treated without surgery. Your plan depends on the grade of the injury, your sport and your goals, and may include:
- Rest, ice, compression and elevation early on, with anti-inflammatory medication if appropriate
- Protection: taping that limits upward bending of the toe, a stiff-soled shoe or a carbon-fiber plate in the shoe for milder injuries, and a walking boot or cast that holds the toe for more severe injuries
- Crutches for a short time if walking is painful
- Physical therapy to restore big-toe motion and rebuild strength in the foot and calf, followed by a gradual return to running, cutting and sport-specific drills
What about PRP? Some athletes ask about platelet-rich plasma (PRP) injections. There is very little published research on PRP for turf toe, so its benefit for this injury is unproven. PRP is generally not FDA-approved for this use and is often not covered by insurance. Dr. Dold will discuss honestly whether it has any role in your situation.
When is surgery needed?
Surgery is considered mainly for severe, grade III injuries, especially when the joint is unstable, the sesamoids have retracted or fractured, there is a loose piece of bone or cartilage in the joint, the toe has started to drift or cock up, or pain and weakness persist despite a full course of non-surgical care. During surgery, the torn plantar plate and capsule are repaired back to the base of the toe, and any associated injury to the sesamoids or cartilage is addressed.
Published results of surgical repair are generally favorable, although the studies are small. In 15 high school and college football players who had surgery for grade III turf toe, the average time lost from play was 16.5 weeks, with low pain scores and good function scores at about 2 years.3 In a 2025 series, 19 of 21 athletes (90.5%) returned to their pre-injury level of competition, on average 20.4 weeks after surgery.4 Individual results vary.
Recovery and return to sport
How long turf toe takes to heal depends mostly on its severity. In the NCAA football study, where most injuries were mild, players missed an average of about 10 days.2 A meta-analysis of 121 turf toe injuries found that athletes treated without surgery returned to sport after a median of about 6 weeks, while those treated with surgery returned after a median of about 15 weeks. Grade III injuries took the longest, a median of 16.5 weeks.5
Return to sport is usually allowed when the toe has enough pain-free upward motion to push off, strength is restored and you can run, cut and jump without limping. Coming back too early can lead to ongoing pain, stiffness or arthritis of the big-toe joint (hallux rigidus). Taping or a stiff insert is often used for a period after returning.
Prevention
Shoes with a stiffer forefoot, or a stiff insert in the shoe, limit how far the big toe can bend and may lower the risk of turf toe, particularly on artificial turf. Athletes who have had turf toe before often use taping or a stiff insert when they return to play.
Related pages:Foot and ankle conditions · Ankle sprains · Achilles tendon rupture
What the research shows
Turf toe has a smaller research base than many sports injuries, and most studies are case series and reviews rather than randomized trials. Here is what the available evidence shows.
Most turf toe heals without surgery
In large college and professional football data, fewer than 2% of turf toe injuries needed surgery. Treatment for most is protection, a stiff-soled shoe or plate insert, and a phased rehabilitation program. Surgery is considered for unstable joints with complete plantar plate tears, sesamoid injuries or bone fragments, which is why careful examination and MRI matter for more severe sprains.
Return to sport
NFL players with turf toe missed about 5 weeks on average, and studies have found their performance after returning was similar to before the injury. After surgical repair of a grade 3 injury, most athletes return to their previous level, typically around 4 to 5 months after surgery.
Playing surface
Most studies comparing playing surfaces have found more foot and ankle injuries on artificial turf than on natural grass, which fits with how the injury got its name.
Why see Dr. Dold
- Board certified by the American Board of Orthopaedic Surgery, with subspecialty certification in Sports Medicine
- Sports medicine and arthroscopy fellowship at NYU Langone / Hospital for Joint Diseases; orthopedic residency at the University of Toronto
- Fellow of the American College of Surgeons (FACS), the American Academy of Orthopaedic Surgeons (FAAOS), the American Orthopaedic Association (FAOA) and the Royal College of Surgeons of Canada (FRCSC)
- Sole author of Acute Achilles Tendon Ruptures: An Update on Current Management Strategies (JAAOS, 2024)
- Team physician and surgical consultant to Rugby Canada; has cared for professional athletes from the NFL, NBA, NHL, MLS, PGA Tour and Major League Rugby
- D Magazine Best Doctors (Collin County), 2019–2026 · Rated 4.9 on Google
Frequently asked questions
What is turf toe?
Turf toe is a sprain of the big-toe joint caused by forceful upward bending of the toe, which stretches or tears the plantar plate and capsule on the underside of the joint.1
Why is it called turf toe?
The injury became well known in football players on artificial turf, where it is more common than on natural grass.2 It can happen on any surface.
How long does turf toe take to heal?
It depends on the grade. Mild sprains may settle in days to a few weeks. In one meta-analysis, athletes treated without surgery returned to sport after a median of about 6 weeks, and those with surgery after about 15 weeks.5 Individual recovery varies.
Can I play with turf toe?
Some athletes with a mild sprain keep playing with taping and a stiff shoe insert. Playing through a more severe injury can make it worse, so a toe that is very swollen, bruised or unstable should be evaluated first.
Do I need surgery for turf toe?
Most turf toe injuries heal without surgery. Surgery is considered for some severe grade III tears, especially when the joint is unstable or the sesamoids have moved out of place.
Is turf toe the same as a broken toe?
No. Turf toe is a ligament and capsule injury, but it can occur with a small fracture or a sesamoid injury. X-rays help tell them apart.
Do you accept my insurance?
Dr. Dold accepts most major insurance plans, including Medicare and Tricare. Please call 469-850-0680 to confirm your coverage.
Research cited on this page
- McCormick JJ, Anderson RB. Turf toe: anatomy, diagnosis, and treatment. Sports Health. 2010;2(6):487-494. PubMed
- George E, Harris AHS, Dragoo JL, et al. Incidence and risk factors for turf toe injuries in intercollegiate football: data from the National Collegiate Athletic Association injury surveillance system. Foot Ankle Int. 2014;35(2):108-115. PubMed
- Smith K, Waldrop N. Operative Outcomes of Grade 3 Turf Toe Injuries in Competitive Football Players. Foot Ankle Int. 2018;39(9):1076-1081. PubMed
- Cho D, Kukadia S, Josephson B, et al. Return to Sport and Radiographic Postoperative Outcomes After Grade 3 Turf Toe Surgical Repair. Am J Sports Med. 2025;53(8):1988-1995. PubMed
- Vopat ML, Hassan M, Poppe T, et al. Return to Sport After Turf Toe Injuries: A Systematic Review and Meta-analysis. Orthop J Sports Med. 2019;7(10):2325967119875133. PubMed
- Seow D, Tengku Yusof TNB, Yasui Y, et al. Treatment Options for Turf Toe: A Systematic Review. J Foot Ankle Surg. 2020;59(1):112-116. PubMed
A systematic review found turf toe studies are few and low in quality, with no evidence-based treatment guideline yet; restricted upward motion of the toe was the most common complication. - Gupta A, Singh PK, Xu AL, et al. Turf Toe Injuries in the Athlete: an Updated Review of Treatment Options, Rehabilitation Protocols, and Return-to-Play Outcomes. Curr Rev Musculoskelet Med. 2023;16(11):563-574. PubMed
A 2023 review reported that fewer than 2% of turf toe injuries need surgery; non-surgical rehab runs up to about 10 weeks and post-surgical rehab up to about 20 weeks. - Waldrop NE. Assessment and Treatment of Sports Injuries to the First Metatarsophalangeal Joint. Foot Ankle Clin. 2021;26(1):1-12. PubMed
A review found most turf toe injuries heal with rest, protection and rehabilitation, while unstable injuries with torn plantar restraints may need repair. - Clough TM, Majeed H. Turf Toe Injury – Current Concepts and an Updated Review of Literature. Foot Ankle Clin. 2018;23(4):693-701. PubMed
A review emphasized early recognition and imaging so severe turf toe injuries are not missed. - Ashimolowo T, Dunham G, Sharp JW, et al. Turf Toe: An Update and Comprehensive Review. Radiol Clin North Am. 2018;56(6):847-858. PubMed
A review summarized the anatomy of the big-toe joint and the spectrum of turf toe injuries. - Perry MT, Pierce JL. Imaging of Turf Toe. Clin Sports Med. 2021;40(4):755-764. PubMed
A review of turf toe imaging described how MRI shows the plantar plate, sesamoids and associated injuries. - Crain JM, Phancao JP. Imaging of Turf Toe. Radiol Clin North Am. 2016;54(5):969-78. PubMed
A radiology review described X-ray and MRI findings across the range of turf toe injuries. - Schein AJ, Skalski MR, Patel DB, et al. Turf toe and sesamoiditis: what the radiologist needs to know. Clin Imaging. 2015;39(3):380-9. PubMed
A radiology review covered imaging of turf toe and sesamoid injuries. - Nery C, Fonseca LF, Gonçalves JP, et al. First MTP joint instability – Expanding the concept of “Turf-toe” injuries. Foot Ankle Surg. 2020;26(1):47-53. PubMed
A series of first MTP joint instability injuries found a range of injury mechanisms and large improvement in toe function scores at about 4.5 years after treatment. - Drakos MC, Fiore R, Murphy C, et al. Plantar-plate disruptions: “the severe turf-toe injury.” three cases in contact athletes. J Athl Train. 2015;50(5):553-60. PubMed
A case series of severe turf toe in contact athletes highlighted stress testing to decide on surgery and stiff-soled or plate-reinforced shoes for protection. - Tran A, Kappa J, Smith E, et al. The Effect of Turf Toe Injuries on Player Performance in the National Football League. Iowa Orthop J. 2019;39(2):35-39. PubMed
NFL players returned after about 5 weeks on average, and performance a year later was similar to uninjured controls. - Madi NS, Parekh TJ, Parekh SG. Outcome of Turf Toe Injuries in NFL Players. J Foot Ankle Surg. 2023;62(1):115-119. PubMed
In NFL running backs and wide receivers, performance after turf toe was not significantly lower than before the injury. - Hsu AR, Anderson RB. Foot and Ankle Injuries in American Football. Am J Orthop (Belle Mead NJ). 2016;45(6):358-367. PubMed
A review of foot and ankle injuries in American football discussed individualized treatment for turf toe and related injuries. - Robertson GAJ, Goffin JS, Wood AM. Return to sport following stress fractures of the great toe sesamoids: a systematic review. Br Med Bull. 2017;122(1):135-149. PubMed
For stress fractures of the big-toe sesamoids, 2–6 months of non-surgical care is usually tried before fixation or sesamoid removal. - Gould HP, Lostetter SJ, Samuelson ER, et al. Lower Extremity Injury Rates on Artificial Turf Versus Natural Grass Playing Surfaces: A Systematic Review. Am J Sports Med. 2023;51(6):1615-1621. PubMed
A review of 53 studies found most reported higher foot and ankle injury rates on artificial turf than on natural grass. - Ranson C, George J, Rafferty J, et al. Playing surface and UK professional rugby union injury risk. J Sports Sci. 2018;36(21):2393-2398. PubMed
In professional rugby, foot injuries were more common on artificial surfaces, although overall injury risk was similar.
Medically reviewed by Andrew P. Dold, MD, FAOA, FAAOS, FACS, FRCSC. Last reviewed October 2026. This page is general information, not medical advice. Individual results vary.


