









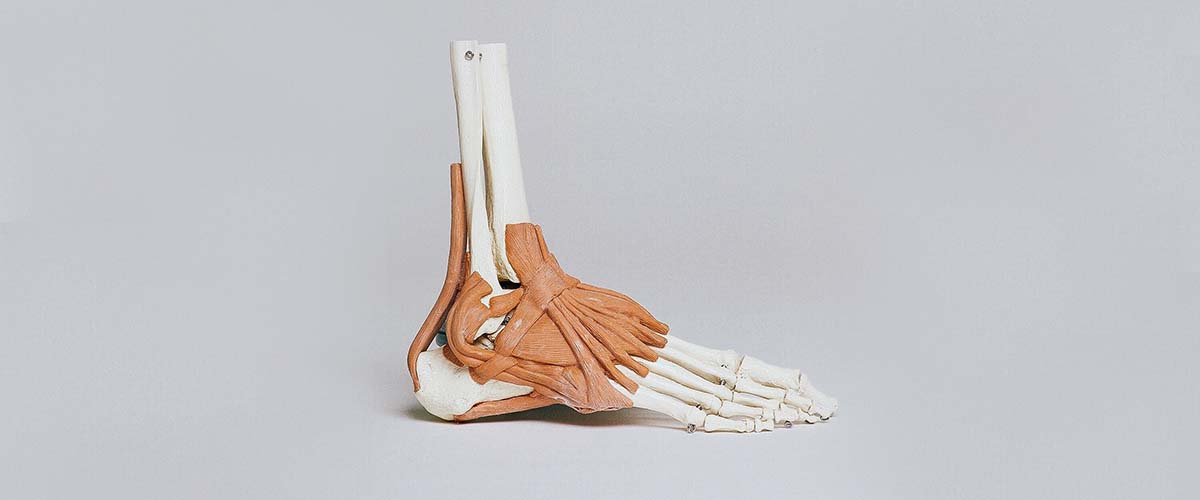
Hallux varus is a deformity in which the big toe points inward, toward the other foot, instead of straight ahead. It is far less common than a bunion (hallux valgus), and in adults it most often appears as a complication after bunion surgery. It can also follow an injury to the ligaments on the outside of the big toe joint, and in rare cases it is present from birth. Many people with a mild inward tilt have no symptoms at all; others have pain, trouble fitting shoes, a toe that catches on footwear, or a joint that becomes stiff and arthritic. Treatment ranges from shoe and taping changes to tendon transfer, osteotomy (bone cut) or joint fusion, chosen according to whether the joint is still flexible and healthy.
- The big toe deviates inward at the big toe joint (first metatarsophalangeal, or MTP, joint)
- Most adult cases follow bunion surgery; reported rates after common bunion procedures are roughly 1–4%
- Mild, flexible deformity is often well tolerated and may need no surgery
- Flexible deformity in a healthy joint can be treated with tendon transfer, tenodesis or a reverse osteotomy
- A stiff or arthritic joint is usually treated with first MTP fusion, which reliably relieves pain
- The research is mostly small case series, so treatment is tailored to each foot
What causes hallux varus?
The big toe joint is held straight by a balance of tendons, ligaments and the two small sesamoid bones underneath it. When that balance tips toward the inside of the foot, the toe drifts inward. Reviews describe several causes:
- After bunion surgery (iatrogenic). This is the most common type in adults. Reported contributors include removing too much of the bump on the metatarsal head, over-correcting the angle between the first and second metatarsals, releasing too much of the tissue on the outside of the joint, over-tightening the tissue on the inside, and removing the outer (fibular) sesamoid. A medially displaced inner sesamoid is a common finding.
- Injury. A tear of the lateral collateral ligament or the adductor tendon on the outside of the joint, sometimes called “gamekeeper’s toe,” can let the toe swing inward. Some of these injuries show up only on stress X-rays.
- Present from birth (congenital). This rare form is often linked to an extra toe (preaxial polydactyly) or to an abnormal growth plate in the first metatarsal called a longitudinal epiphyseal bracket. It is treated by pediatric foot surgeons.
- Inflammatory arthritis, neuromuscular conditions and idiopathic cases. Rheumatoid arthritis and nerve or muscle disorders can unbalance the joint, and a small number of adults develop it without a clear cause.
Symptoms
- The big toe angles toward the other foot, sometimes with the tip curling down (a clawed or “cocked-up” toe)
- Rubbing, calluses or blisters on the inside of the toe from shoes
- Pain at the big toe joint, especially with walking, running or push-off
- Difficulty fitting into closed-toe shoes
- Stiffness or grinding if the joint has become arthritic
- A gap opening between the big toe and second toe
Long-term follow-up suggests that a mild inward tilt after bunion surgery is often well tolerated: in one series followed for an average of 18 years, patients with an average deformity of about 10 degrees mostly rated their results as excellent, and only those with severe deformity were dissatisfied or needed more surgery.
How hallux varus is diagnosed
Diagnosis starts with a history and exam. Dr. Dold checks:
- Flexibility. Can the toe be pushed back to a straight position (a flexible, or reducible, deformity), or is it fixed?
- Joint health. Is motion at the big toe joint painful or grinding, which suggests arthritis?
- Tendon balance. Is the toe pulled into a claw by the long extensor tendon? Is the interphalangeal (tip) joint also deformed?
- Previous surgery. Records from any bunion procedure help explain what changed.
Weight-bearing X-rays measure the hallux valgus angle (negative in varus), the angle between the first and second metatarsals, the position of the sesamoids, signs of arthritis, and any hardware or healed osteotomy. Stress views can reveal a dynamic instability after an injury. These findings drive the treatment plan: published treatment algorithms center on joint flexibility, the condition of the cartilage, soft-tissue balance and any bony deformity.
Non-surgical treatment
Not everyone with hallux varus needs surgery. Options include:
- Wider, deeper shoes with a soft upper to reduce rubbing on the inside of the toe
- Taping or splinting the toe toward a straighter position, mainly useful early after surgery or an injury
- Padding and spacers to protect the skin
- Activity changes and anti-inflammatory medicine for flare-ups
Early taping after bunion surgery is sometimes tried when over-correction is noticed in the first weeks, though evidence for it is limited to clinical experience. If symptoms persist despite these measures, surgery may be considered.
Surgical options for a flexible joint without arthritis
When the joint still moves well and the cartilage is healthy, the goal is to rebalance the toe while preserving motion. Reviews describe several joint-sparing approaches, often combined with release of the tight tissue on the inside of the joint:
- Extensor hallucis longus (EHL) transfer. Rerouting the long extensor tendon beneath the ligament between the first two metatarsals to pull the toe back outward. The original technique also fused the tip joint of the toe; split-tendon versions avoid that fusion.
- Extensor hallucis brevis (EHB) tenodesis. Using the short extensor tendon to recreate the lateral ligament. A biomechanical study showed it restored joint stability, and a small clinical series reported maintained correction at about two years.
- Reverse abductor hallucis transfer. Moving the tendon on the inside of the toe to the outside. Reported satisfaction was about 69% at four years, with some loss of correction over time.
- Suture-button or anchor reconstruction. Implant-based techniques to recreate the outer ligament, described in case reports and technique papers.
- Reverse osteotomy. If the earlier bunion surgery over-corrected the metatarsal, the bone itself can be cut and shifted back (for example a reverse scarf or a distal chevron with a medial wedge), sometimes combined with a tendon transfer.
A systematic review of soft-tissue release combined with tendon transfer for flexible iatrogenic hallux varus found a 4.4% recurrence rate, while also noting how limited the data are.
Surgical options for a stiff or arthritic joint
When the deformity is fixed or the joint is arthritic, first MTP joint fusion (arthrodesis) is the procedure most reviews recommend. The joint is fixed in a corrected position with screws and/or a plate, which eliminates painful motion and keeps the toe straight. In a series of rigid iatrogenic hallux varus treated with fusion, pain scores dropped from about 7 to about 1 out of 10 at roughly five years, with no significant loss of correction. Fusion is also the usual salvage option if a joint-sparing procedure fails. You can learn more about big toe arthritis on our hallux rigidus page.
Recovery
Recovery depends on the procedure. In general:
- Tendon transfer or soft-tissue reconstruction: a protective post-operative shoe or boot for about 6 weeks, with taping or a splint to protect the repair, then a gradual return to normal shoes.
- Osteotomy: similar protection while the bone heals, with X-rays to confirm healing, usually around 6–8 weeks.
- Fusion: protected weight-bearing in a stiff-soled shoe or boot until the bones fuse, often 8–12 weeks, with swelling that can take several months to settle.
Your plan, including when you can drive, return to work and return to sport, will be based on your procedure and how your foot heals.
Why see Dr. Dold
Dr. Dold is a board-certified orthopedic surgeon who treats all foot and ankle conditions, including complex big toe problems and revision of earlier bunion surgery. He evaluates each foot for flexibility, joint health and tendon balance, and explains which options fit your situation, starting with non-surgical care when it is reasonable. Related pages: bunions (hallux valgus), sesamoid injuries and toe fractures and turf toe.
Frequently asked questions
What is the difference between hallux varus and a bunion?
A bunion (hallux valgus) is when the big toe points outward toward the second toe. Hallux varus is the opposite: the big toe points inward, away from the other toes.
How common is hallux varus after bunion surgery?
Published rates vary by procedure. A meta-analysis of the scarf osteotomy reported about 3.4%, and other series report figures from about 1% to 4%. Most cases are mild.
Does hallux varus always need surgery?
No. A mild, flexible inward tilt that does not hurt is often well tolerated long term. Surgery is considered for pain, shoe-wear problems or a progressive deformity.
Can the joint be saved, or will I need a fusion?
If the joint is flexible and the cartilage is healthy, joint-sparing options such as tendon transfer, tenodesis or a reverse osteotomy may be possible. A stiff or arthritic joint is usually treated with fusion.
Will I be able to wear normal shoes after treatment?
Most published series report improved pain and shoe wear after treatment. Swelling can take several months to settle, especially after fusion.
Is hallux varus covered by insurance?
Dr. Dold accepts most major insurance plans, including Medicare and Tricare. Please call 469-850-0680 to confirm your coverage.
Research cited on this page
- Mohan R, Dhotare SV, Morgan SS. Hallux varus: A literature review. Foot (Edinb). 2021;49:101863. PubMed
Literature review: acquired, particularly iatrogenic, hallux varus is the most common type; the main problem is muscle and tendon imbalance at the big toe joint. - Donley BG. Acquired hallux varus. Foot Ankle Int. 1997;18(9):586-92. PubMed
Review: acquired hallux varus most often follows bunion surgery; not all patients require surgery. - Davies MB, Blundell CM. The treatment of iatrogenic hallux varus. Foot Ankle Clin. 2014;19(2):275-84. PubMed
Review: iatrogenic hallux varus usually results from over-resection, over-translation of an osteotomy, over-release laterally or over-tightening medially; it is not always symptomatic, and fusion is the recommended salvage. - Crawford MD, Patel J, Giza E. Iatrogenic hallux varus treatment algorithm. Foot Ankle Clin. 2014;19(3):371-84. PubMed
Treatment algorithm: assessment focuses on joint flexibility, joint integrity, soft-tissue balance and bony deformity; the evidence is mainly retrospective case series. - Piat C, Cazeau C, Stiglitz Y. Post-operative hallux varus: a review of treatment methods. Int Orthop. 2021;45(9):2193-2199. PubMed
Review: choice of treatment depends mainly on range of motion, reducibility of the joint and tendon balance. - Leemrijse T, Devos Bevernage B. Surgical treatment of iatrogenic hallux varus. Orthop Traumatol Surg Res. 2020;106(1S):S159-S170. PubMed
Review: joint-sparing surgery is preferred in flexible deformities and young patients; an over-corrected metatarsal osteotomy should also be revised. - Devos Bevernage B, Leemrijse T. Hallux varus: classification and treatment. Foot Ankle Clin. 2009;14(1):51-65. PubMed
Review: classification and treatment require comprehensive radiographic and clinical assessment. - Trnka HJ, Zettl R, Hungerford M, et al. Acquired hallux varus and clinical tolerability. Foot Ankle Int. 1997;18(9):593-7. PubMed
Long-term follow-up (average 18 years): average deformity about 10 degrees was well tolerated; only patients with extreme deformity were dissatisfied or needed further surgery. - Sieloff MR, Tokarski AR, Elliott AD, et al. The Incidence of Complications Following Scarf Osteotomy for the Treatment of Hallux Valgus: A Systematic Review With Meta-Analysis. J Foot Ankle Surg. 2023;62(4):610-617. PubMed
Systematic review and meta-analysis of scarf osteotomy: hallux varus rate about 3.4%. - Dayton P, Sedberry S, Feilmeier M. Complications of metatarsal suture techniques for bunion correction: a systematic review of the literature. J Foot Ankle Surg. 2015;54(2):230-2. PubMed
Systematic review of metatarsal suture-button techniques for bunions: hallux varus in 3.8% of the Mini TightRope group. - Mann RA, Pfeffinger L. Hallux valgus repair. DuVries modified McBride procedure. Clin Orthop Relat Res. 1991(272):213-8. PubMed
Modified McBride bunion repair: six patients developed hallux varus (average 7.5 degrees), all with medial displacement of the tibial sesamoid. - Akhtar S, Malek S, Hariharan K. Hallux varus following scarf osteotomy. Foot (Edinb). 2016;29:1-5. PubMed
Hallux varus occurred after about 1% of scarf osteotomies in one surgical series; a classification and management approach are proposed. - Saxena A, Krisdakumtorn T. Return to activity after sesamoidectomy in athletically active individuals. Foot Ankle Int. 2003;24(5):415-9. PubMed
Sesamoidectomy in active patients: the one case of hallux varus followed fibular (outer) sesamoid removal. - Turner RS. Dynamic post-surgical hallux varus after lateral sesamoidectomy: treatment and prevention. Orthopedics. 1986;9(7):963-9. PubMed
Report of dynamic hallux varus after lateral sesamoidectomy, describing the procedure as risky. - Johnson KA, Spiegl PV. Extensor hallucis longus transfer for hallux varus deformity. J Bone Joint Surg Am. 1984;66(5):681-6. PubMed
EHL transfer beneath the intermetatarsal ligament with IP joint fusion gave overall satisfactory correction in 15 toes. - Myerson MS, Komenda GA. Results of hallux varus correction using an extensor hallucis brevis tenodesis. Foot Ankle Int. 1996;17(1):21-7. PubMed
EHB tenodesis: correction maintained in all six patients at a mean of 28 months, with a slight decrease in dorsiflexion. - Juliano PJ, Myerson MS, Cunningham BW. Biomechanical assessment of a new tenodesis for correction of hallux varus. Foot Ankle Int. 1996;17(1):17-20. PubMed
Biomechanical study: EHB tenodesis restored resistance to varus displacement after lateral structures were divided. - Plovanich EJ, Donnenwerth MP, Abicht BP, et al. Failure after soft-tissue release with tendon transfer for flexible iatrogenic hallux varus: a systematic review. J Foot Ankle Surg. 2012;51(2):195-7. PubMed
Systematic review: soft-tissue release with tendon transfer for flexible iatrogenic hallux varus; 4.4% recurrence, all after the Johnson EHL transfer with IP fusion. - Schwagten K, Vandeputte G, Somville J, et al. Long term clinical results of hallux varus correction by a reversed abductor hallucis transfer. Foot Ankle Surg. 2020;26(7):777-783. PubMed
Reverse abductor hallucis transfer: 69% success satisfaction at a mean of 48 months; long-term loss of correction is possible. - Leemrijse T, Hoang B, Maldague P, et al. A new surgical procedure for iatrogenic hallux varus: reverse transfer of the abductor hallucis tendon: a report of 7 cases. Acta Orthop Belg. 2008;74(2):227-34. PubMed
Reverse abductor hallucis transfer in 7 feet: AOFAS hallux score improved from 61 to 88 at over two years. - Koh DTS, Chong KW, Yeo NEM. Hallux Varus Correction With Extensor Hallucis Longus Tendon Transfer and Reverse Scarf Osteotomy. Foot Ankle Spec. 2021;14(4):352-360. PubMed
EHL transfer with or without reverse scarf osteotomy: pain scores fell from 5 to 1 and all patients were satisfied at 24 months (small series). - Gerbert J, Traynor C, Blue K, et al. Use of the Mini TightRope® for correction of hallux varus deformity. J Foot Ankle Surg. 2011;50(2):245-51. PubMed
Technique report describing use of a suture-button device to correct acquired hallux varus. - Piat C, Raboudi T, Cazeau C, et al. Postoperative Hallux Varus Treatment by Reverse Scarf Osteotomy. Foot Ankle Int. 2021;42(8):976-981. PubMed
Reverse scarf osteotomy: median AOFAS improved from 47 to 79 and pain from 6.7 to 2.3; all bones healed. - Choi KJ, Lee HS, Yoon YS, et al. Distal metatarsal osteotomy for hallux varus following surgery for hallux valgus. J Bone Joint Surg Br. 2011;93(8):1079-83. PubMed
Distal chevron osteotomy with medial wedge and medial release in 19 feet: AOFAS improved from 77 to 95; two recurrences. - Skalley TC, Myerson MS. The operative treatment of acquired hallux varus. Clin Orthop Relat Res. 1994(306):183-91. PubMed
Operative treatment of acquired hallux varus (tendon transfers, fusion, resection arthroplasty): pain, shoe-wear problems and instability improved in all groups at 3.8 years. - Tourné Y, Saragaglia D, Picard F, et al. Iatrogenic hallux varus surgical procedure: a study of 14 cases. Foot Ankle Int. 1995;16(8):457-63. PubMed
Series of 14 cases: ligament reconstruction with medial release for supple joints, fusion for stiff or arthritic joints; good to excellent scores in both groups. - Belfiore S, Vaggi S, Vitali F, et al. Rigid iatrogenic hallux varus: a decades’ worth experience with arthrodesis of the metatarsophalangeal joint. Int Orthop. 2024;48(11):2923-2929. PubMed
Rigid iatrogenic hallux varus treated with first MTP fusion: pain improved from 7.3 to 1.3 at about 5.5 years with no significant loss of correction. - Hoveidaei AH, Roshanshad A, Vosoughi AR. Clinical and radiological outcomes after arthrodesis of the first metatarsophalangeal joint. Int Orthop. 2021;45(3):711-719. PubMed
First MTP fusion series: fusion rate 97.9%; the hallux varus group had the most favourable outcomes. - Mills JA, Menelaus MB. Hallux varus. J Bone Joint Surg Br. 1989;71(3):437-40. PubMed
Hallux varus series with 12.7-year follow-up: soft-tissue procedures satisfactory in 12 of 17 feet; MTP fusion also satisfactory. - Shim JS, Lim TK, Koh KH, et al. Surgical treatment of congenital hallux varus. Clin Orthop Surg. 2014;6(2):216-22. PubMed
Congenital hallux varus: surgical correction gave favourable overall outcomes; a longitudinal epiphyseal bracket should be considered as a cause. - Choo AD, Mubarak SJ. Longitudinal epiphyseal bracket. J Child Orthop. 2013;7(6):449-54. PubMed
Review: longitudinal epiphyseal bracket most commonly appears in the foot as hallux varus. - Granberry WM, Hickey CH. Idiopathic adult hallux varus. Foot Ankle Int. 1994;15(4):197-205. PubMed
Report of idiopathic adult hallux varus, with discussion of possible causes. - Schmitt P, Piana L, Gosey GM, et al. Gamekeeper’s Toe: A Case Series and Review of Surgically Treated Traumatic Hallux Varus Due to Lateral Collateral Ligament Injury. Foot Ankle Orthop. 2025;10(4):24730114251405256. PubMed
Traumatic lateral collateral ligament injury of the big toe (gamekeeper’s toe): patients returned to high-level athletics after repair. - Monteagudo M, Martínez-de-Albornoz P. Management of Complications After Hallux Valgus Reconstruction. Foot Ankle Clin. 2020;25(1):151-167. PubMed
Review of complications after bunion reconstruction: overcorrection (hallux varus) is among the commonly reported complications.
Medically reviewed by Andrew P. Dold, MD, FAOA, FAAOS, FACS, FRCSC. Last reviewed October 2026. This page is general information, not medical advice. Your own diagnosis and treatment plan depend on your exam and imaging.


