









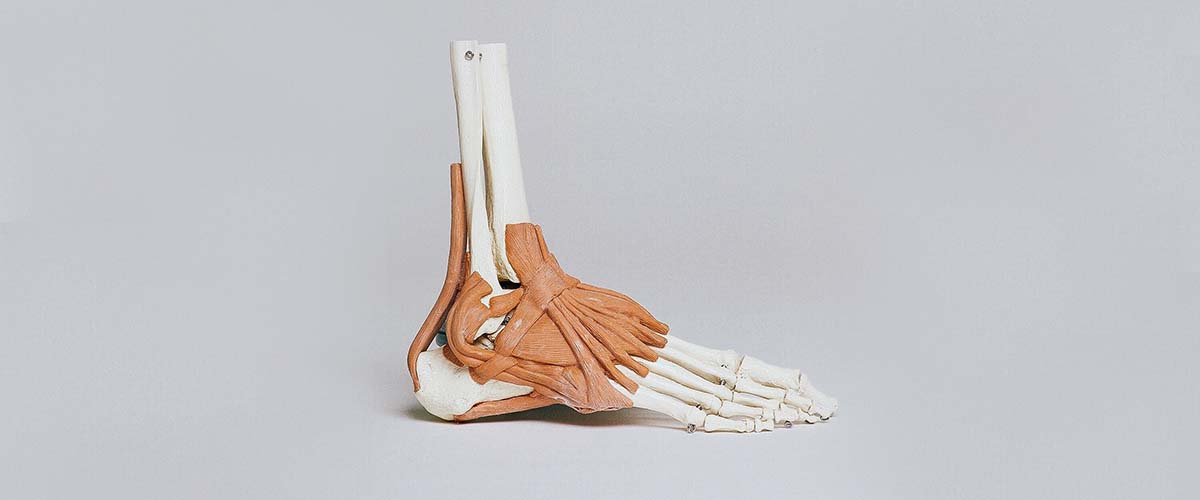
Anterior ankle impingement is pain at the front of the ankle when the shin and the top of the foot pinch together, as in squatting, lunging, landing or climbing stairs. It is caused by bone spurs on the front of the tibia or talus (sometimes called footballer’s ankle) or by thickened scar and synovial tissue, often after repeated sprains.1,4 It is a common cause of chronic ankle pain in athletes, and arthroscopic treatment gives good results with low complication rates.11,19
- Pain at the front of the ankle with deep bending (lunging, squatting, sprinting, stairs)
- Bony spurs or scar tissue, often after repeated sprains1,4
- Oblique X-rays and MRI help confirm it2,9
- Most improve with rehab and activity changes first1
- Arthroscopic debridement relieves pain in most; results are better without arthritis12,19
Types
- Bony (anterior or anteromedial) impingement: spurs on the front of the tibia and talus, from repetitive impact and pushing the ankle into deep dorsiflexion.1,18
- Soft-tissue (anterolateral) impingement: thickened synovium and scar tissue in the outer gutter of the ankle, usually after a sprain and often with some instability.4
- Bassett ligament impingement: a separate lower band of the anterior tibiofibular ligament that can rub on the talus.6 A thickened band has been linked to cartilage lesions that MRI can miss.8
Symptoms
- Pain at the front of the ankle with lunging, squatting, sprinting, uphill running or stairs
- Reduced ability to bend the ankle upward
- Swelling after activity
- Tenderness over the front or front-outer ankle
Diagnosis
Dr. Dold examines tenderness and motion and checks for ankle instability. Standard X-rays can miss spurs on the inner side, so an oblique view is recommended.2 MRI shows soft-tissue thickening, cartilage damage and ligament injury;10,24 it can miss soft-tissue impingement (42% sensitivity in one study),23 so the exam remains central. Dynamic ultrasound can also help.9
Non-surgical treatment
Initial treatment includes activity modification, physical therapy and strengthening, a brace and anti-inflammatory medicines.1 A cortisone injection can help confirm the diagnosis and calm inflamed tissue. Underlying ankle instability is addressed with balance and strengthening work.9
Arthroscopic surgery
When symptoms persist, arthroscopy removes the spurs and inflamed or scarred tissue through two small incisions:2,5
- Arthroscopic treatment provides good patient satisfaction with low complication rates.11
- Removing tibiotalar spurs gives good to excellent results in most patients with rapid recovery.18 Results were good or excellent in 77% of ankles with early arthritis and 53% with moderate arthritis, and some spurs recurred.12
- For soft-tissue impingement, 26 of 31 patients had good or excellent results and returned to sport at about 6 weeks,20 pooled scores averaged 90.1,21 and scores improved from 59 to 88.22 Higher BMI and male sex predicted less improvement.13
- A lateral ligament repair can be added if the ankle is unstable.5 Outcomes are less favorable with instability or joint-space narrowing,19 and arthritis is a key prognostic factor.3 See ankle arthritis.
In-office needle arthroscopy is a newer option with early promising results,14 though evidence is still limited.15 Dr. Dold performs ankle arthroscopy in the operating room and can discuss a referral if you are interested in needle arthroscopy. Across nearly 8,000 ankle arthroscopies, major complications occurred in only 0.2%;16 rare problems include nerve irritation and, very rarely, a blood-vessel injury after removing large spurs.17
Recovery
- Walking in a boot or shoe as comfortable within days, with early motion encouraged.1
- Return to sport often around 6 weeks after soft-tissue debridement,20 sometimes longer after larger spur removal.
Dr. Dold reviews your timeline based on your findings.
Frequently asked questions
What is footballer’s ankle?
Bone spurs at the front of the ankle from repeated impact and deep bending, common in soccer players and other athletes. The spurs pinch tissue when the ankle bends upward.
Do bone spurs need to be removed?
Not always. Spurs that don’t cause pain can be left alone. Surgery is considered when they limit motion and cause pain despite rehab.
Can scar tissue after a sprain cause ongoing pain?
Yes. Thickened tissue in the front-outer ankle can pinch with movement after a sprain and is a common cause of lingering pain.
How long is recovery after ankle arthroscopy?
Many people walk within days and return to sport in about 6 weeks after soft-tissue debridement, with longer recovery after larger procedures.
Will the spurs come back?
Some regrow over time, but most patients keep their pain relief, especially when there is no significant arthritis.
Research cited on this page
- Talusan PG, Toy J, Perez JL, et al. Anterior ankle impingement: diagnosis and treatment. J Am Acad Orthop Surg. 2014;22(5):333-9. PubMed
Anterior ankle impingement is first treated with activity modification, bracing and anti-inflammatories; early motion and weight-bearing are advised after surgery. - Tol JL, van Dijk CN. Anterior ankle impingement. Foot Ankle Clin. 2006;11(2):297-310, vi. PubMed
Arthroscopic removal of soft-tissue overgrowth and bone spurs is effective for anterior impingement when the joint space is not narrowed. - Ross KA, Murawski CD, Smyth NA, et al. Current concepts review: Arthroscopic treatment of anterior ankle impingement. Foot Ankle Surg. 2017;23(1):1-8. PubMed
Outcomes of arthroscopic treatment for anteromedial and anterolateral impingement are favorable, and arthritis is a prognostic factor. - Shane AM, Reeves CL, Vazales R, et al. Soft Tissue Impingement of the Ankle: Pathophysiology, Evaluation, and Arthroscopic Treatment. Clin Podiatr Med Surg. 2016;33(4):503-20. PubMed
Soft-tissue impingement is most often anterolateral and frequently follows ankle sprains with instability. - Leiber-Wackenheim F. Anterior ankle impingement. Orthop Traumatol Surg Res. 2025;111(1S):104063. PubMed
Treatment removes bone spurs and inflamed soft tissue, sometimes with ligament repair, with clear improvement in pain and function. - Bassett FH, Gates HS, Billys JB, et al. Talar impingement by the anteroinferior tibiofibular ligament. A cause of chronic pain in the ankle after inversion sprain. J Bone Joint Surg Am. 1990;72(1):55-9. PubMed
A separate fascicle of the anteroinferior tibiofibular ligament (Bassett ligament) can impinge on the talus; removing it usually relieves pain. - Subhas N, Vinson EN, Cothran RL, et al. MRI appearance of surgically proven abnormal accessory anterior-inferior tibiofibular ligament (Bassett’s ligament). Skeletal Radiol. 2008;37(1):27-33. PubMed
An abnormal Bassett ligament can be seen on MRI, but associated cartilage damage is poorly detected. - Butler JJ, Randall GW, Dalmau-Pastor M, et al. A hypertrophic distal fascicle of the anterior tibiofibular ligament is associated with a high rate of osteochondral lesions of the talus. Knee Surg Sports Traumatol Arthrosc. 2024;32(9):2452-2462. PubMed
A thickened distal fascicle of this ligament was linked to cartilage lesions of the talus that MRI often missed. - Yang M, Fei X, Li F, et al. Systematic review of anterior ankle impingement: subtype-specific diagnosis & intervention. J Foot Ankle Surg. 2026;65(5):172.e1-172.e7. PubMed
Oblique X-rays, MRI and dynamic ultrasound help diagnose impingement; management depends on the subtype. - Zbojniewicz AM. Impingement syndromes of the ankle and hindfoot. Pediatr Radiol. 2019;49(12):1691-1701. PubMed
Impingement syndromes are one cause of persistent ankle pain after injury, and imaging supports the clinical diagnosis. - Zwiers R, Wiegerinck JI, Murawski CD, et al. Arthroscopic Treatment for Anterior Ankle Impingement: A Systematic Review of the Current Literature. Arthroscopy. 2015;31(8):1585-96. PubMed
Arthroscopic treatment for anterior ankle impingement provides good patient satisfaction with low complication rates. - Tol JL, Verheyen CP, van Dijk CN. Arthroscopic treatment of anterior impingement in the ankle. J Bone Joint Surg Br. 2001;83(1):9-13. PubMed
Results were good or excellent in 77% with early arthritis and 53% with moderate arthritis; some spurs recurred. - Buda R, Baldassarri M, Parma A, et al. Arthroscopic Treatment and Prognostic Classification of Anterior Soft Tissue Impingement of the Ankle. Foot Ankle Int. 2016;37(1):33-9. PubMed
Arthroscopic debridement was effective for anterior soft-tissue impingement; higher BMI and male sex predicted worse results. - Colasanti CA, Mercer NP, Garcia JV, et al. In-Office Needle Arthroscopy for the Treatment of Anterior Ankle Impingement Yields High Patient Satisfaction With High Rates of Return to Work and Sport. Arthroscopy. 2022;38(4):1302-1311. PubMed
In-office needle arthroscopy for anterior impingement reduced pain with high return to work and sport. - Burt J, Smith V, Gee CW, et al. The role of outpatient needle arthroscopy in the diagnosis and management of musculoskeletal complaints: A systematic review of the Arthrex NanoScope. Knee. 2023;42:246-257. PubMed
Needle arthroscopy shows promise, but the evidence is still small and low quality. - Arshad Z, Aslam A, Al Shdefat S, et al. Complications following ankle arthroscopy. Bone Joint J. 2023;105-B(3):239-246. PubMed
Across 7,942 ankle arthroscopies, major complications occurred in 0.2%; most complications were minor. - Yammine K, Kheir N, Daher J, et al. Pseudoaneurysm following ankle arthroscopy: a systematic review of case series. Eur J Orthop Surg Traumatol. 2019;29(3):689-696. PubMed
Rarely, a pseudoaneurysm can follow ankle arthroscopy, particularly after removing large anterior spurs. - Dujela MD, Houng BE. Arthroscopic Treatment of Anterior Ankle Impingement. Clin Podiatr Med Surg. 2023;40(3):397-411. PubMed
Arthroscopic removal of tibiotalar bone spurs gives good to excellent results in most patients, with rapid recovery. - Jacobson K, Ng A, Haffner KE. Arthroscopic treatment of anterior ankle impingement. Clin Podiatr Med Surg. 2011;28(3):491-510. PubMed
Arthroscopic debridement gives favorable results, though outcomes may be less favorable with instability or joint narrowing. - Ferkel RD, Karzel RP, Del Pizzo W, et al. Arthroscopic treatment of anterolateral impingement of the ankle. Am J Sports Med. 1991;19(5):440-6. PubMed
Arthroscopic treatment of anterolateral impingement gave 26 of 31 good or excellent results, with return to sport at about 6 weeks. - Katakura M, Odagiri H, Charpail C, et al. Arthroscopic treatment for anterolateral impingement of the ankle: Systematic review and exploration of evidence about role of ankle instability. Orthop Traumatol Surg Res. 2022;108(7):103159. PubMed
Across 203 patients, arthroscopic treatment of anterolateral impingement averaged an AOFAS score of 90.1. - Mardani-Kivi M, Mirbolook A, Khajeh-Jahromi S, et al. Arthroscopic treatment of patients with anterolateral impingement of the ankle with and without chondral lesions. J Foot Ankle Surg. 2013;52(2):188-91. PubMed
Arthroscopic treatment improved AOFAS scores from 59.2 to 88.1 at 6 months. - Farooki S, Yao L, Seeger LL. Anterolateral impingement of the ankle: effectiveness of MR imaging. Radiology. 1998;207(2):357-60. PubMed
Conventional MRI had 42% sensitivity and 85% specificity for anterolateral impingement. - Jordan LK, Helms CA, Cooperman AE, et al. Magnetic resonance imaging findings in anterolateral impingement of the ankle. Skeletal Radiol. 2000;29(1):34-9. PubMed
MRI showed a soft-tissue mass in the anterolateral gutter in all patients with impingement.
Medically reviewed by Andrew P. Dold, MD, FAOA, FAAOS, FACS, FRCSC. Last reviewed October 2026. This page is general information, not medical advice. Your own diagnosis and treatment plan depend on your exam and imaging.


