








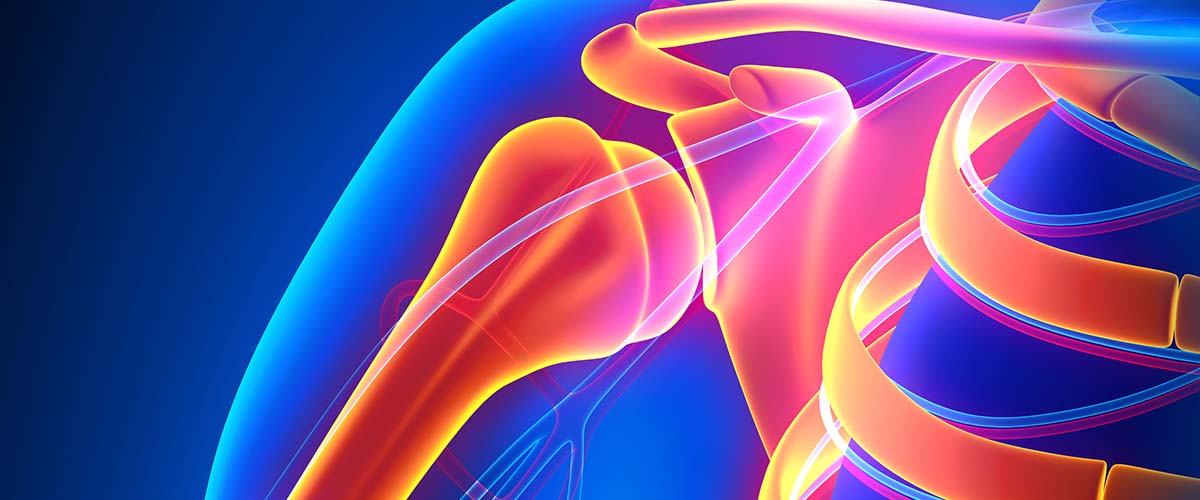
Shoulder arthritis (glenohumeral osteoarthritis) is wear of the smooth cartilage covering the ball and socket of the shoulder joint. It causes pain, stiffness, grinding and loss of motion. The shoulder is the third most commonly affected large joint after the knee and hip.1 Dr. Andrew Dold, a board-certified, fellowship-trained sports medicine surgeon in Frisco, Texas, treats shoulder arthritis with non-surgical care and joint-preserving arthroscopic surgery, especially for younger and active patients. If you have failed conservative care, a total or reverse shoulder replacement may be a great option for you.
- Physical therapy, activity changes and anti-inflammatory medicine are the first steps
- Cortisone, PRP and hyaluronic acid injections can relieve pain but do not reverse arthritis
- Arthroscopic “CAM” surgery can delay replacement in carefully selected younger patients
- If conservative care fails, a total or reverse shoulder replacement may be a great option
Symptoms
- Deep, aching shoulder pain, often worse with activity and at night
- Stiffness and loss of motion, especially reaching behind the back or overhead
- Grinding, clicking or catching
Diagnosis
Dr. Dold examines shoulder motion and strength and reviews X-rays, which show joint-space narrowing, bone spurs and the shape of the socket. An MRI or CT scan may be used to check the rotator cuff and the bone, especially when planning surgery. If the rotator cuff is also torn, the arthritis pattern is different; see rotator cuff arthropathy.
Treatment without surgery
- Physical therapy to maintain motion and strengthen the rotator cuff and shoulder-blade muscles2
- Activity modification to reduce painful loading
- Anti-inflammatory medicines (NSAIDs), which are usually the first-line medication if safe for you2
Injections
Injections can relieve pain, but none of them stops or reverses arthritis.2
- Cortisone can relieve pain and inflammation for a period of time.
- Hyaluronic acid (gel): in a multicenter randomized trial, patients with shoulder osteoarthritis had significantly better pain relief through 26 weeks than with saline, although the study missed its primary 13-week end point.3 Overall, the evidence for hyaluronic acid in the shoulder is mixed,2 and its use in the shoulder is off-label in the United States.
- Platelet-rich plasma (PRP) is a promising option, especially for younger patients who want to delay surgery, but more research is needed to define its role.1 Dr. Dold has published a systematic review of PRP for cartilage damage and arthritis4 and will discuss the realistic benefits with you.
The American Academy of Orthopaedic Surgeons has published an evidence-based guideline on the management of shoulder osteoarthritis that reviews these options.5
Arthroscopic joint-preserving surgery
For younger or active patients who are not ready for a replacement, Dr. Dold performs arthroscopic debridement and the more extensive Comprehensive Arthroscopic Management (CAM) procedure. Through small incisions, the joint is cleaned of loose cartilage and loose bodies, inflamed lining is removed, bone spurs are trimmed, tight capsule is released and, when needed, the biceps tendon is treated.6
CAM is considered a bridging procedure. Reported survivorship (not needing a replacement) is about 92% at 1 year, 85% at 2 years, 77% at 5 years and 63% at 10 years.6 Results are less durable in patients with very little joint space left (under about 2 mm), more advanced arthritis, age over 50 or certain abnormal socket shapes.7 A systematic review found improved motion and pain with few complications, but rates of later conversion to replacement ranged widely (4% to 42%) and benefits may fade over time.8 Compared with replacement in young patients, arthroscopic debridement had fewer complications.9 Careful patient selection is essential.
Shoulder replacement
If you have failed conservative care and your arthritis is advanced, an anatomic total shoulder replacement (TSA) or a reverse shoulder replacement may be a great option for you. Dr. Dold will review your X-rays, rotator cuff and goals with you to help decide on the right next step.
What the research shows
Here is what the research adds about shoulder arthritis treatment.
Injections
Hyaluronic acid has shown modest but consistent pain relief in pooled studies, although placebo injections also help many patients. In a randomized trial, PRP and hyaluronic acid gave similar improvements over a year. If shoulder replacement is likely, timing matters: cortisone injections close to surgery have been linked to a higher risk of infection after replacement.
Arthroscopic joint preservation
Arthroscopic procedures, including comprehensive arthroscopic management (CAM), can improve motion and pain and delay replacement in carefully selected younger patients, particularly those with milder arthritis. Some patients still go on to replacement, so it is often viewed as a bridge to replacement.
Shoulder replacement
Total shoulder replacement gives better function than replacing the ball alone. For patients with an intact rotator cuff, both anatomic and reverse replacements work well: reverse replacement has had fewer complications in recent analyses, while anatomic replacement preserves more rotation. Younger patients under 50 have also done well after anatomic replacement, and most patients return to recreational sports such as golf, swimming and tennis.
Why see Dr. Dold
- Board certified by the American Board of Orthopaedic Surgery, with subspecialty certification in Sports Medicine
- Sports medicine and arthroscopy fellowship at NYU Langone / Hospital for Joint Diseases; orthopedic residency at the University of Toronto
- Fellow of the American College of Surgeons (FACS), the American Academy of Orthopaedic Surgeons (FAAOS), the American Orthopaedic Association (FAOA) and the Royal College of Surgeons of Canada (FRCSC)
- Author of a SLAP repair book chapter (Springer, 2017) and research on shoulder suture anchors (KSSTA, 2013)
- Team physician and surgical consultant to Rugby Canada; has cared for professional athletes from the NFL, NBA, NHL, MLS, PGA Tour and Major League Rugby
- D Magazine Best Doctors (Collin County), 2019–2026 · Rated 4.9 on Google
Frequently asked questions
Can shoulder arthritis be treated without surgery?
Yes. Physical therapy, activity changes, anti-inflammatory medicines and injections help many patients control their symptoms.2
Do injections cure shoulder arthritis?
No. Cortisone, hyaluronic acid and PRP can reduce pain, but none of them stops or reverses arthritis.2
What is the CAM procedure?
Comprehensive Arthroscopic Management is a joint-preserving arthroscopic surgery that cleans out the joint, removes bone spurs and releases tight tissue. It can delay replacement in well-selected patients.6
How long does a CAM procedure last?
In published results, about 77% of patients had not needed a replacement at 5 years and 63% at 10 years.6
When should I consider shoulder replacement?
If your pain and function are not improving despite conservative care and your arthritis is advanced, a total or reverse shoulder replacement may be a great option for you.
Research cited on this page
- Rossi LA, Piuzzi NS, Shapiro SA. Glenohumeral Osteoarthritis: The Role for Orthobiologic Therapies: Platelet-Rich Plasma and Cell Therapies. JBJS Rev. 2020;8(2):e0075. PubMed
- Yamamoto N, Szymski D, Voss A, et al. Non-operative management of shoulder osteoarthritis: Current concepts. J ISAKOS. 2023;8(5):289-295. PubMed
- Blaine T, Moskowitz R, Udell J, et al. Treatment of persistent shoulder pain with sodium hyaluronate: a randomized, controlled trial. A multicenter study. J Bone Joint Surg Am. 2008;90(5):970-979. PubMed
- Dold AP, Zywiel MG, Taylor DW, Dwyer T, Theodoropoulos J. Platelet-rich plasma in the management of articular cartilage pathology: a systematic review. Clin J Sport Med. 2014;24(1):31-43. PubMed
- Khazzam MS, Pearl ML. AAOS Clinical Practice Guideline: Management of Glenohumeral Joint Osteoarthritis. J Am Acad Orthop Surg. 2020;28(19):790-794. PubMed
- Arner JW, Ruzbarsky JJ, Millett PJ. Comprehensive Arthroscopic Management of Shoulder Arthritis. Arthroscopy. 2022;38(4):1035-1036. PubMed
- Mitchell JJ, Warner BT, Horan MP, et al. Comprehensive Arthroscopic Management of Glenohumeral Osteoarthritis: Preoperative Factors Predictive of Treatment Failure. Am J Sports Med. 2017;45(4):794-802. PubMed
- Williams BT, Beletsky A, Kunze KN, et al. Outcomes and Survivorship After Arthroscopic Treatment of Glenohumeral Arthritis: A Systematic Review. Arthroscopy. 2020;36(7):2010-2021. PubMed
- Sayegh ET, Mascarenhas R, Chalmers PN, et al. Surgical Treatment Options for Glenohumeral Arthritis in Young Patients: A Systematic Review and Meta-analysis. Arthroscopy. 2015;31(6):1156-1166.e8. PubMed
- Zhang B, Thayaparan A, Horner N, et al. Outcomes of hyaluronic acid injections for glenohumeral osteoarthritis: a systematic review and meta-analysis. J Shoulder Elbow Surg. 2019;28(3):596-606. PubMed
A meta-analysis found hyaluronic acid injections reduced shoulder arthritis pain at 3 and 6 months, though control groups also improved, suggesting a placebo effect. - Migliorini F, Schäfer L, Masoni V, et al. Intra-articular injections for shoulder arthritis in adults: a systematic review. Eur J Med Res. 2025;30(1):1080. PubMed
A 2025 review found injections can give symptomatic relief in shoulder arthritis, with hyaluronic acid showing consistent but modest benefit. - Kirschner JS, Cheng J, Creighton A, et al. Efficacy of Ultrasound-Guided Glenohumeral Joint Injections of Leukocyte-Poor Platelet-Rich Plasma Versus Hyaluronic Acid in the Treatment of Glenohumeral Osteoarthritis: A Randomized, Double-Blind Controlled Trial. Clin J Sport Med. 2022;32(6):558-566. PubMed
In a randomized trial, a single PRP injection and a hyaluronic acid injection gave similar improvements in shoulder arthritis over 12 months. - Schoell K, Crabb R, Simpson E, et al. Preoperative corticosteroid injections are associated with a higher periprosthetic infection rate following primary total shoulder arthroplasty: a systematic review and meta-analysis. J Shoulder Elbow Surg. 2024;33(12):2734-2742. PubMed
Cortisone injections before shoulder replacement were linked to a higher risk of joint infection, especially when given close to surgery. - Denard PJ, Wirth MA, Orfaly RM. Management of glenohumeral arthritis in the young adult. J Bone Joint Surg Am. 2011;93(9):885-92. PubMed
A review found arthroscopic debridement most likely to help patients with mild arthritis, small cartilage lesions and involvement of only one side of the joint. - Saltzman BM, Leroux TS, Verma NN, et al. Glenohumeral Osteoarthritis in the Young Patient. J Am Acad Orthop Surg. 2018;26(17):e361-e370. PubMed
A review of shoulder arthritis in young patients described arthroscopic debridement and other joint-preserving options once non-surgical care is exhausted. - Millett PJ, Fritz EM, Frangiamore SJ, et al. Arthroscopic Management of Glenohumeral Arthritis: A Joint Preservation Approach. J Am Acad Orthop Surg. 2018;26(21):745-752. PubMed
A review described the comprehensive arthroscopic management (CAM) procedure and its role in delaying replacement in younger patients. - Carver DC, Brolin TJ. Arthroscopic Management of Glenohumeral Arthritis. Orthop Clin North Am. 2019;50(4):521-528. PubMed
Arthroscopic joint-preserving treatment can delay shoulder replacement in younger patients while maintaining function. - Craig RS, Goodier H, Singh JA, et al. Shoulder replacement surgery for osteoarthritis and rotator cuff tear arthropathy. Cochrane Database Syst Rev. 2020;4(4):CD012879. PubMed
A Cochrane review found no high-quality trials comparing shoulder replacement with other treatments for osteoarthritis. - Singh JA, Sperling J, Buchbinder R, et al. Surgery for shoulder osteoarthritis. Cochrane Database Syst Rev. 2010(10):CD008089. PubMed
A Cochrane review found total shoulder replacement gave better function than replacing only the ball (hemiarthroplasty). - Daher M, Boufadel P, Fares MY, et al. Reverse versus anatomic total shoulder arthroplasty for glenohumeral osteoarthritis with intact cuff: a meta-analysis of clinical outcomes. J Shoulder Elbow Surg. 2025;34(1):190-202. PubMed
A 2025 meta-analysis of patients with an intact rotator cuff found reverse replacement had fewer complications and reoperations than anatomic replacement, with less rotation. - Gupta MS, Krishan A, Rashid A, et al. Reverse versus anatomic total shoulder arthroplasty in patients over 70 with a competent rotator cuff and glenohumeral osteoarthritis: a meta-analysis. J Shoulder Elbow Surg. 2026;35(5):1370-1386. PubMed
In patients 70 and older with an intact cuff, anatomic replacement gave better rotation than reverse replacement, with similar patient-reported outcomes. - Lauck BJ, Cathey JM, Adams NC, et al. Why do primary anatomic total shoulder arthroplasties fail today? A systematic review and meta-analysis. J Shoulder Elbow Surg. 2025;34(12):2746-2759. PubMed
Across more than 35,000 anatomic shoulder replacements, loosening of the socket component was the most common reason for failure. - Peebles LA, Akamefula RA, Weinerman J, et al. Anatomic total shoulder arthroplasty indications, outcomes, and survivorship in patients younger than 50 years of age: a systematic review. J Shoulder Elbow Surg. 2026;35(5):1360-1369. PubMed
In patients under 50, anatomic total shoulder replacement substantially improved motion and outcomes. - Liu JN, Steinhaus ME, Garcia GH, et al. Return to sport after shoulder arthroplasty: a systematic review and meta-analysis. Knee Surg Sports Traumatol Arthrosc. 2018;26(1):100-112. PubMed
Most patients returned to sports such as swimming, golf and tennis after shoulder replacement, with the highest rate after anatomic replacement.
Medically reviewed by Andrew P. Dold, MD, FAOA, FAAOS, FACS, FRCSC. Last reviewed October 2026. This page is general information, not medical advice. Individual results vary.

