









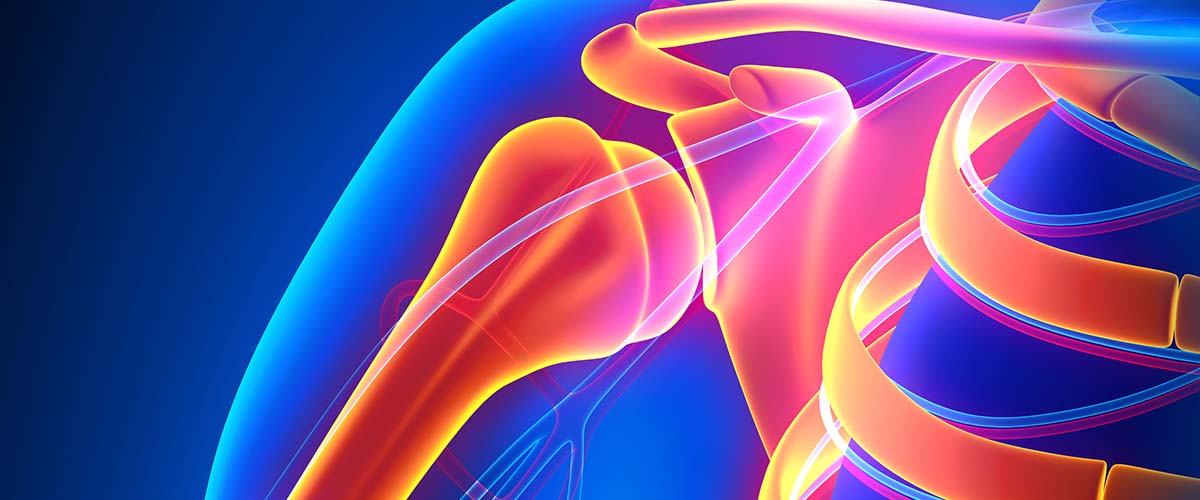
The acromioclavicular (AC) joint is the small joint at the top of the shoulder where the collarbone (clavicle) meets the shoulder blade (acromion). Two common problems cause pain here: AC joint arthritis, wear of the joint cartilage that becomes more common with age or after an old AC separation, and distal clavicle osteolysis, a stress injury to the end of the collarbone seen mainly in weightlifters. Dr. Andrew Dold, a board-certified, fellowship-trained sports medicine surgeon in Frisco, Texas, treats both, starting with non-surgical care and, when needed, arthroscopic distal clavicle excision.
- Pain is felt on top of the shoulder and is worse reaching across the body, lifting overhead or bench pressing
- Activity changes, anti-inflammatory medicine and an injection into the joint help many patients
- An injection of numbing medicine also helps confirm that the AC joint is the source of pain
- For pain that persists, a small portion of the end of the collarbone can be removed arthroscopically
Causes
- Wear and tear (osteoarthritis): the cartilage gradually thins, and bone spurs can form
- Previous injury: an earlier AC joint separation or fracture near the joint can lead to arthritis later
- Distal clavicle osteolysis: repeated heavy loading, especially bench press, dips and overhead lifting, causes tiny stress fractures and bone breakdown at the end of the collarbone. It was first reported as a series in weight trainers in 1982.1
Symptoms
- Pain directly on top of the shoulder, which you can often point to with one finger
- Pain reaching across the body, such as fastening a seat belt or washing the opposite armpit
- Pain with bench press, push-ups, dips or overhead lifting
- Pain lying on the affected shoulder
- A bump or swelling over the joint
Diagnosis
Dr. Dold checks for tenderness over the AC joint and pain when the arm is brought across the body, and examines the rotator cuff and biceps, which often cause pain at the same time. X-rays show narrowing, spurs or bone loss at the end of the collarbone. An MRI may show swelling in the bone (common in osteolysis) and other shoulder problems.1 A diagnostic injection of numbing medicine into the AC joint can confirm the source of pain: if the pain goes away, the AC joint is the likely cause.
Treatment without surgery
- Activity changes: avoid or modify the painful lifts for a period, for example by narrowing the bench-press grip, limiting depth or switching exercises
- Ice and anti-inflammatory medicine, if safe for you
- Physical therapy to strengthen the shoulder and shoulder-blade muscles
- A cortisone injection into the AC joint to reduce pain
For osteolysis, avoiding the provocative movements, modifying weight-training technique, ice and anti-inflammatory medicine form the basis of initial treatment.1
Surgery: distal clavicle excision
When pain persists despite non-surgical treatment and the AC joint is confirmed as the source, Dr. Dold may recommend a distal clavicle excision: a small portion of the end of the collarbone is removed so the bones no longer rub, while the ligaments that keep the collarbone stable are preserved. It can be done arthroscopically through small incisions, and it can be combined with other procedures such as a rotator cuff repair.
In a systematic review of 17 studies, arthroscopic distal clavicle excision had success rates over 90%, more good or excellent outcomes than the open procedure and a faster return to activities, with similar long-term results. Results were less predictable when the joint was unstable from a previous injury.2
Recovery
After arthroscopic distal clavicle excision, most patients use a sling briefly for comfort and start moving the shoulder early, then progress with strengthening. Heavy pressing and overhead lifting are resumed gradually over the following months. Dr. Dold will give you a specific plan.
What the research shows
- Diagnosis: AC joint changes are very common on X-ray and MRI, even in people without pain, so imaging alone is not enough. Tenderness over the joint, pain with cross-body reach, and relief after a small injection of numbing medicine into the joint are more reliable signs that the AC joint is the source.
- Injections: a corticosteroid injection into the AC joint provides meaningful relief for many patients. Ultrasound guidance makes the injection more accurate.
- Most patients do well without surgery: activity changes (such as modifying bench press, dips and push-ups for weightlifters), anti-inflammatory medicine and injections help most people. Reviews find conservative and surgical treatment both effective.
- Distal clavicle resection removes a small amount of bone from the end of the collarbone when symptoms persist. Studies report good or excellent results in most patients. Arthroscopic and open techniques give similar results, and arthroscopy may allow a faster return to activity and lets the surgeon check the rest of the shoulder.
- Arthritis without symptoms: several randomized trials show that removing the end of the collarbone during rotator cuff repair, when the AC joint is not painful, does not improve results and can cause instability. It is done only when the AC joint itself is causing pain.
Why see Dr. Dold
- Board certified by the American Board of Orthopaedic Surgery, with subspecialty certification in Sports Medicine
- Sports medicine and arthroscopy fellowship at NYU Langone / Hospital for Joint Diseases; orthopedic residency at the University of Toronto
- Fellow of the American College of Surgeons (FACS), the American Academy of Orthopaedic Surgeons (FAAOS), the American Orthopaedic Association (FAOA) and the Royal College of Surgeons of Canada (FRCSC)
- Author of a SLAP repair book chapter (Springer, 2017) and research on shoulder suture anchors (KSSTA, 2013)
- Team physician and surgical consultant to Rugby Canada; has cared for professional athletes from the NFL, NBA, NHL, MLS, PGA Tour and Major League Rugby
- D Magazine Best Doctors (Collin County), 2019–2026 · Rated 4.9 on Google
Frequently asked questions
What is the difference between an AC separation and AC arthritis?
An AC separation is a ligament injury, usually from a fall. AC arthritis is wear of the joint cartilage, which can develop over time or after an old separation.
Why does my shoulder hurt when I bench press?
Bench press, dips and push-ups load the AC joint heavily. In weightlifters, this can cause distal clavicle osteolysis, a stress injury to the end of the collarbone.1
Will I have to stop lifting?
Usually not permanently. Modifying the painful lifts for a period, along with ice and anti-inflammatory medicine, is the first step.1
Does removing the end of the collarbone weaken the shoulder?
Only a small portion of bone is removed and the stabilizing ligaments are preserved. Success rates over 90% have been reported after arthroscopic excision.2
How long is recovery?
Most patients start moving the shoulder early after arthroscopic excision, with a gradual return to heavy lifting over the following months.
Do you accept my insurance?
Dr. Dold accepts most major insurance plans, including Medicare and Tricare. Please call 469-850-0680 to confirm your coverage.
Considering surgery? Read about shoulder arthroscopy in Frisco, the minimally invasive procedure Dr. Dold uses for rotator cuff, labral and biceps problems.
Research cited on this page
- Schwarzkopf R, Ishak C, Elman M, et al. Distal clavicular osteolysis: a review of the literature. Bull NYU Hosp Jt Dis. 2008;66(2):94-101. PubMed
- Pensak M, Grumet RC, Slabaugh MA, et al. Open versus arthroscopic distal clavicle resection. Arthroscopy. 2010;26(5):697-704. PubMed
- Krill MK, Rosas S, Kwon K, et al. A concise evidence-based physical examination for diagnosis of acromioclavicular joint pathology: a systematic review. Phys Sportsmed. 2018;46(1):98-104. PubMed
Systematic review: no combination of exam tests reliably confirms AC joint problems on its own; the Paxinos sign with O’Brien’s test is the most useful combination. - Ibounig T, Rämö L, Haas R, et al. Imaging abnormalities of the acromioclavicular joint and subacromial space are common in asymptomatic shoulders: a systematic review. J Orthop Surg Res. 2025;20(1):7. PubMed
Systematic review: AC joint abnormalities on imaging are common in shoulders without symptoms, often as common as in painful shoulders. - Shaffer BS. Painful conditions of the acromioclavicular joint. J Am Acad Orthop Surg. 1999;7(3):176-88. PubMed
Review: a diagnostic injection improves accuracy; most patients improve without surgery, though those with osteolysis may need to modify activities. - Peck E, Lai JK, Pawlina W, et al. Accuracy of ultrasound-guided versus palpation-guided acromioclavicular joint injections: a cadaveric study. PM R. 2010;2(9):817-21. PubMed
Cadaver study: ultrasound-guided AC joint injection is highly accurate compared with palpation. - Rijs Z, de Groot PCJ, Zwitser EW, et al. Is the Anterior Injection Approach Without Ultrasound Guidance Superior to the Posterior Approach for Adhesive Capsulitis of the Shoulder? A Sequential, Prospective Trial. Clin Orthop Relat Res. 2021;479(11):2483-2489. PubMed
Equivalence study: a new anterior injection approach without ultrasound was nearly as accurate as ultrasound-guided injection. - Sabeti-Aschraf M, Stotter C, Thaler C, et al. Intra-articular versus periarticular acromioclavicular joint injection: a multicenter, prospective, randomized, controlled trial. Arthroscopy. 2013;29(12):1903-10. PubMed
Randomized trial: AC joint injection gave a highly significant clinical benefit with both ultrasound-guided and other techniques. - Daley EL, Bajaj S, Bisson LJ, et al. Improving injection accuracy of the elbow, knee, and shoulder: does injection site and imaging make a difference? A systematic review. Am J Sports Med. 2011;39(3):656-62. PubMed
Systematic review: imaging guidance improves the accuracy of shoulder injections. - Soler F, Mocini F, Djemeto DT, et al. No differences between conservative and surgical management of acromioclavicular joint osteoarthritis: a scoping review. Knee Surg Sports Traumatol Arthrosc. 2021;29(7):2194-2201. PubMed
Scoping review: conservative and surgical treatments are both effective for AC joint arthritis. - DeFroda SF, Nacca C, Waryasz GR, et al. Diagnosis and Management of Distal Clavicle Osteolysis. Orthopedics. 2017;40(2):119-124. PubMed
Review: patients who fail conservative care may benefit from distal clavicle resection, open or arthroscopic. - Rios CG, Mazzocca AD. Acromioclavicular joint problems in athletes and new methods of management. Clin Sports Med. 2008;27(4):763-88. PubMed
Review: AC joint problems in athletes arise from trauma, arthritis or distal clavicle osteolysis. - Rabalais RD, McCarty E. Surgical treatment of symptomatic acromioclavicular joint problems: a systematic review. Clin Orthop Relat Res. 2007;455:30-7. PubMed
Systematic review: distal clavicle resection gives predominantly good or excellent results; arthroscopic resection reported more good results in low-level studies. - Hohmann E, Tetsworth K, Glatt V. Open versus arthroscopic acromioclavicular joint resection: a systematic review and meta-analysis. Arch Orthop Trauma Surg. 2019;139(5):685-694. PubMed
Meta-analysis: open and arthroscopic distal clavicle resection produce similar functional and clinical outcomes. - Charron KM, Schepsis AA, Voloshin I. Arthroscopic distal clavicle resection in athletes: a prospective comparison of the direct and indirect approach. Am J Sports Med. 2007;35(1):53-8. PubMed
Randomized trial: direct and indirect arthroscopic approaches both give successful outcomes. - Freedman BA, Javernick MA, O’Brien FP, et al. Arthroscopic versus open distal clavicle excision: comparative results at six months and one year from a randomized, prospective clinical trial. J Shoulder Elbow Surg. 2007;16(4):413-8. PubMed
Randomized trial: arthroscopic and open distal clavicle resection both improved pain; arthroscopy also identified other joint problems. - Oh JH, Kim JY, Choi JH, et al. Is arthroscopic distal clavicle resection necessary for patients with radiological acromioclavicular joint arthritis and rotator cuff tears? A prospective randomized comparative study. Am J Sports Med. 2014;42(11):2567-73. PubMed
Randomized trial: preventive distal clavicle resection for arthritis without symptoms during cuff repair did not improve outcomes and caused instability in some. - Gallinet D, Barth J, Labattut L, et al. Benefits of distal clavicle resection during rotator cuff repair: Prospective randomized single-blind study. Orthop Traumatol Surg Res. 2020;106(8S):S207-S211. PubMed
Randomized trial: routine distal clavicle resection with rotator cuff repair is not recommended. - Wang J, Ma JX, Zhu SW, et al. Does Distal Clavicle Resection Decrease Pain or Improve Shoulder Function in Patients With Acromioclavicular Joint Arthritis and Rotator Cuff Tears? A Meta-analysis. Clin Orthop Relat Res. 2018;476(12):2402-2414. PubMed
Meta-analysis: distal clavicle resection during cuff repair did not improve outcomes and may cause AC joint instability. - Park YB, Koh KH, Shon MS, et al. Arthroscopic distal clavicle resection in symptomatic acromioclavicular joint arthritis combined with rotator cuff tear: a prospective randomized trial. Am J Sports Med. 2015;43(4):985-90. PubMed
Randomized trial: combined distal clavicle resection and cuff repair gave no better results than cuff repair alone at 2 years. - Kim J, Chung J, Ok H. Asymptomatic acromioclavicular joint arthritis in arthroscopic rotator cuff tendon repair: a prospective randomized comparison study. Arch Orthop Trauma Surg. 2011;131(3):363-9. PubMed
Randomized trial: resection with cuff repair for arthritis without symptoms caused early pain without long-term benefit. - Thorsen EHK, Dalbøge A, Hovgaard N, et al. Occupational mechanical exposures as risk factor for shoulder osteoarthritis: a systematic review. Ann Work Expo Health. 2024;68(9):895-905. PubMed
Systematic review: occupational mechanical exposures are associated with AC joint arthritis (low-certainty evidence). - Haupt HA. Upper extremity injuries associated with strength training. Clin Sports Med. 2001;20(3):481-90. PubMed
Review: distal clavicle osteolysis is among the upper-extremity injuries associated with strength training.
Medically reviewed by Andrew P. Dold, MD, FAOA, FAAOS, FACS, FRCSC. Last reviewed October 2026. This page is general information, not medical advice. Individual results vary.


