









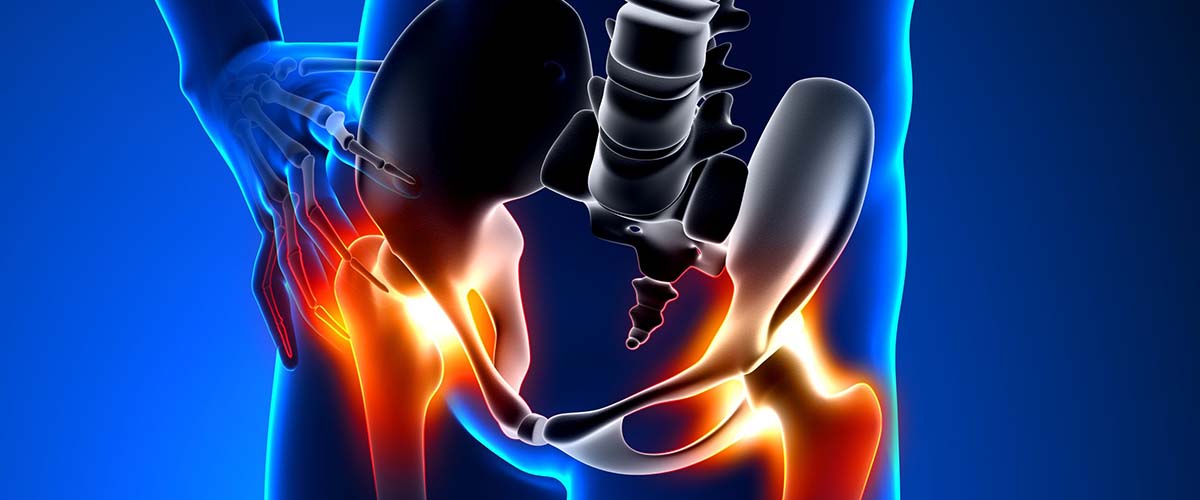
A hip fracture is a break in the upper part of the thighbone (femur), just below the ball of the hip joint. Most hip fractures happen in older adults after a fall, often because osteoporosis (thinning of the bones) has made the bone fragile. A different type of hip fracture, the femoral neck stress fracture, can develop in runners and other athletes from repeated stress rather than a single fall. Dr. Andrew Dold is a board-certified, fellowship-trained sports medicine surgeon in Frisco, Texas. If you have hip pain after a fall or a suspected stress fracture, Dr. Dold’s office can help you get evaluated; for an acute injury after a fall, go to the emergency room.
- The 3 main types are femoral neck, intertrochanteric and subtrochanteric fractures
- Nearly all hip fractures in older adults are treated with surgery, and guidelines suggest surgery within 24 to 48 hours of admission
- Depending on the fracture, the bone is fixed with screws, a plate or a rod, or the broken part is replaced with a partial or total hip replacement
- Getting up and walking soon after surgery is a key part of recovery
- After a hip fracture, bone density testing, osteoporosis treatment and fall prevention help lower the risk of another fracture
Types of hip fractures
- Femoral neck fractures occur in the narrow “neck” just below the ball. Because the blood supply to the ball runs along the neck, a displaced (shifted) femoral neck fracture can damage it, which raises the risk that the bone will not heal or that the ball will collapse (avascular necrosis).
- Intertrochanteric fractures occur a little lower, between the two bony bumps where the large hip muscles attach. This area has a good blood supply and usually heals well once it is fixed.
- Subtrochanteric fractures occur just below those bumps, in the upper shaft of the femur. This area is under high stress, so these fractures need strong fixation.
Symptoms
- Severe pain in the hip or groin after a fall
- Inability to stand, walk or put weight on the leg
- A leg that looks shorter than the other or is turned outward
- Bruising and swelling around the hip
Some fractures, especially stress fractures or small cracks that have not shifted, cause milder pain and still allow walking. Groin or hip pain that does not go away after a fall, or that keeps getting worse with activity, should be checked.
Diagnosis
Hip fractures are usually diagnosed with X-rays. If X-rays look normal but a fracture is still suspected, an MRI (or sometimes a CT scan) can show a hidden fracture. In older adults, the care team also checks the heart, lungs, blood tests and medications so the patient can safely have surgery.
Why surgery is usually done within 24 to 48 hours
Nearly all hip fractures in older adults are treated with surgery, because lying in bed for weeks while a fracture heals carries serious risks such as pneumonia, blood clots, bedsores and loss of strength. The American Academy of Orthopaedic Surgeons (AAOS) guideline states that hip fracture surgery within 24 to 48 hours of admission may be associated with better outcomes.1,2 A meta-analysis of 28 studies with more than 31,000 older patients found that surgery within 48 hours was associated with about a 20% lower risk of death within 12 months and fewer complications.3 Some patients need a short delay first to treat a medical problem, such as a heart issue or a blood thinner, so they can go through surgery safely.
Surgery options
The right operation depends on the type of fracture, how much it has shifted, the quality of the bone, the health of the hip joint and how active the person was before the injury.
- Internal fixation (repair): screws, a plate and screw, or a rod placed inside the femur hold the bone in place while it heals. This is commonly used for femoral neck fractures that have not shifted and for intertrochanteric fractures. For unstable intertrochanteric fractures and subtrochanteric fractures, the AAOS guideline recommends a rod-type implant (a cephalomedullary nail) placed down the center of the femur.1
- Hemiarthroplasty (partial hip replacement): the broken ball and neck are replaced with a metal implant, while the patient’s own socket is kept. For displaced femoral neck fractures in older adults, the AAOS guideline recommends replacement (arthroplasty) over fixation.1
- Total hip replacement: both the ball and the socket are replaced. For properly selected patients with displaced femoral neck fractures, often those who were active and walking independently or who already had hip arthritis, the AAOS guideline notes there may be a functional benefit to total hip replacement over partial replacement, at the risk of more complications.1 Learn more about anterior hip replacement and hip arthritis.
Younger adults with femoral neck fractures, usually from high-energy injuries, are generally treated with urgent fixation to try to save their own hip.
Recovery and rehabilitation
Recovery starts the day after surgery, or even the same day. After surgical treatment of a hip fracture, the AAOS guideline says that immediate full weight bearing as tolerated may be considered.1 Getting out of bed and walking early, with a walker and help from physical therapists, lowers the risks of being bedbound and helps restore independence.
Many older adults spend time in a rehabilitation center or skilled nursing facility before going home, and physical therapy often continues for several months. Recovery is often slower than after a planned hip replacement, and not everyone regains the same level of walking or independence they had before the fracture. Individual results vary.
Preventing the next fracture
A hip fracture from a simple fall is often the first sign of osteoporosis, and it raises the risk of another fracture. Steps to lower that risk include:
- Bone density testing and osteoporosis treatment: ask your doctor about a bone density (DEXA) scan and medication. In a large randomized trial of 2,127 patients who had recently had hip fracture surgery, a yearly zoledronic acid infusion (an osteoporosis medication) lowered the rate of new clinical fractures from 13.9% to 8.6%, a 35% reduction, and deaths were also lower in the treated group (9.6% vs 13.3%).4
- Calcium and vitamin D as recommended by your doctor
- Exercise for balance and strength: a Cochrane review of 108 randomized trials found that exercise programs reduced the rate of falls in older adults living in the community by about 23%, with balance and functional exercises and multi-part programs showing the clearest benefit.5
- Fall-proofing the home: good lighting, removing loose rugs and clutter, grab bars in the bathroom, and having vision and medications that cause dizziness reviewed
Femoral neck stress fractures in athletes
A stress fracture is a crack that develops from repeated loading, without a single injury. In the hip it most often affects the femoral neck, and is seen in distance runners, military recruits and athletes who rapidly increase their training. Low energy availability (not eating enough for the training load), menstrual irregularities and low bone density raise the risk.
The typical symptom is a deep ache in the groin or front of the hip that comes on with running and gradually worsens, sometimes with pain at rest or at night. X-rays are often normal early on, so an MRI is usually needed to make the diagnosis.
Femoral neck stress fractures should be taken seriously. Delayed diagnosis can allow the fracture to shift, which may lead to failure of the bone to heal or loss of blood supply to the ball (avascular necrosis), with long-term problems.6 Small stress fractures on the inner (compression) side of the neck are often treated with crutches and a period of no running, followed by a gradual return. Fractures on the outer (tension) side, larger fractures and any fracture that has shifted are usually treated with surgical screw fixation. If you are a runner with groin pain that worsens with activity, stop running and get evaluated.
Related pages:Hip conditions · Hip pain · Hip replacement questions
What the research shows
- Timely surgery and team care: surgery within about 24–48 hours, once the patient is medically ready, is the standard. A large trial found that accelerating surgery to within hours of diagnosis did not reduce deaths overall, but delays beyond 2 days are linked to higher mortality. Co-management with geriatric medicine lowers complications and mortality.
- Femoral neck fractures: for displaced fractures in older adults, replacing the femoral head (arthroplasty) leads to fewer repeat operations than fixing the fracture with screws. In the HEALTH trial, total hip replacement and hemiarthroplasty had similar reoperation rates, with slightly better function but more dislocations after total hip replacement, so the choice depends on activity level and health. Cemented stems improved quality of life and reduced fractures around the implant compared with uncemented stems.
- Intertrochanteric fractures: sliding hip screws and intramedullary nails have similar outcomes for stable fractures; nails are favored for unstable patterns.
- Prevent the next fracture: a hip fracture signals osteoporosis. In the HORIZON trial, a yearly zoledronic acid infusion after hip fracture repair reduced new fractures and improved survival without affecting healing, so bone health treatment is part of the plan.
Why see Dr. Dold
- Board certified by the American Board of Orthopaedic Surgery, with subspecialty certification in Sports Medicine
- Sports medicine and arthroscopy fellowship at NYU Langone / Hospital for Joint Diseases; orthopedic residency at the University of Toronto
- Fellow of the American College of Surgeons (FACS), the American Academy of Orthopaedic Surgeons (FAAOS), the American Orthopaedic Association (FAOA) and the Royal College of Surgeons of Canada (FRCSC)
- Published research on hip arthroscopy, including Post-operative Considerations Following Hip Arthroscopy (JBJS Reviews, 2017) and studies in the American Journal of Sports Medicine; member of the International Society for Hip Arthroscopy (ISHA)
- Team physician and surgical consultant to Rugby Canada; has cared for professional athletes from the NFL, NBA, NHL, MLS, PGA Tour and Major League Rugby
- D Magazine Best Doctors (Collin County), 2019–2026 · Rated 4.9 on Google
Frequently asked questions
What should I do if I think someone has broken a hip?
Call 911 or go to the nearest emergency room. Keep the person still and comfortable, and do not try to make them walk.
Can you walk with a broken hip?
Most people cannot, but some people with a small crack or a stress fracture can still walk with pain. Ongoing hip or groin pain after a fall should be checked with X-rays and sometimes an MRI.
Why is hip fracture surgery done so quickly?
Surgery within 24 to 48 hours of admission may be associated with better outcomes,1 and early surgery has been associated with lower mortality and fewer complications in older adults.3
Will I need a hip replacement or a repair?
It depends on the type and position of the fracture, your bone quality and your activity level. Displaced femoral neck fractures in older adults are usually treated with partial or total hip replacement, while many other fractures are fixed with screws, a plate or a rod.1
How long is recovery after a hip fracture?
Most people walk with a walker within a day or two of surgery, but full recovery often takes several months of physical therapy. Individual results vary.
How can I prevent another hip fracture?
Ask about bone density testing and osteoporosis treatment, stay active with balance and strength exercises, and make your home safer to reduce falls.4,5
Do you accept my insurance?
Dr. Dold accepts most major insurance plans, including Medicare and Tricare. Please call 469-850-0680 to confirm your coverage.
Think you have a fracture? See fracture care in Frisco: same-day appointments and walk-ins Monday, Wednesday and Friday, 8:30–10:30 am.
Research cited on this page
- American Academy of Orthopaedic Surgeons. Management of Hip Fractures in Older Adults: Evidence-Based Clinical Practice Guideline. Published December 3, 2021. aaos.org/hipfxcpg
- O’Connor MI, Switzer JA. AAOS Clinical Practice Guideline Summary: Management of Hip Fractures in Older Adults. J Am Acad Orthop Surg. 2022;30(20):e1291-e1296. DOI
- Klestil T, Röder C, Stotter C, et al. Impact of timing of surgery in elderly hip fracture patients: a systematic review and meta-analysis. Sci Rep. 2018;8(1):13933. PubMed
- Lyles KW, Colón-Emeric CS, Magaziner JS, et al. Zoledronic acid and clinical fractures and mortality after hip fracture. N Engl J Med. 2007;357(18):1799-1809. PubMed
- Sherrington C, Fairhall NJ, Wallbank GK, et al. Exercise for preventing falls in older people living in the community. Cochrane Database Syst Rev. 2019;1(1):CD012424. PubMed
- Cichy B, Roche SJ, Wozniak A. Atypical femoral neck stress fracture in a marathon runner: a case report and literature review. Ir J Med Sci. 2012;181(3):427-429. PubMed
- HIP ATTACK Investigators. Accelerated surgery versus standard care in hip fracture (HIP ATTACK): an international, randomised, controlled trial. Lancet. 2020;395(10225):698-708. PubMed
HIP ATTACK trial (Lancet): accelerated surgery did not lower mortality or major complications compared with standard care. - Borges FK, Guerra-Farfan E, Bhandari M, et al. Myocardial Injury in Patients with Hip Fracture: A HIP ATTACK Randomized Trial Substudy. J Bone Joint Surg Am. 2024;106(24):2303-2312. PubMed
HIP ATTACK analysis: in patients presenting with heart muscle injury, accelerated surgery was associated with lower mortality. - Chang W, Lv H, Feng C, et al. Preventable risk factors of mortality after hip fracture surgery: Systematic review and meta-analysis. Int J Surg. 2018;52:320-328. PubMed
Meta-analysis: surgery delayed more than 2 days, malignancy, nursing home residence and heart, lung and diabetic disease increased mortality. - Guerra-Farfan E, Borges FK, Bhandari M, et al. Mortality, perioperative complications and surgical timelines in hip fracture patients: Comparison of the Spanish with the non-Spanish Cohort of the HIP ATTACK-1 trial. Injury. 2024;55(11):111827. PubMed
HIP ATTACK Spain: 1 in 8 patients died within 90 days; heart injury, infection and delirium were the most common complications. - Grigoryan KV, Javedan H, Rudolph JL. Orthogeriatric care models and outcomes in hip fracture patients: a systematic review and meta-analysis. J Orthop Trauma. 2014;28(3):e49-55. PubMed
Meta-analysis: orthogeriatric co-management improved mortality after hip fracture surgery. - Van Heghe A, Mordant G, Dupont J, et al. Effects of Orthogeriatric Care Models on Outcomes of Hip Fracture Patients: A Systematic Review and Meta-Analysis. Calcif Tissue Int. 2022;110(2):162-184. PubMed
Meta-analysis: orthogeriatric care models were associated with fewer complications and lower mortality. - Bhandari M, Devereaux PJ, Swiontkowski MF, et al. Internal fixation compared with arthroplasty for displaced fractures of the femoral neck. A meta-analysis. J Bone Joint Surg Am. 2003;85(9):1673-81. PubMed
Meta-analysis: for displaced femoral neck fractures, arthroplasty reduced revision surgery compared with internal fixation. - HEALTH Investigators, Bhandari M, Einhorn TA, et al. Total Hip Arthroplasty or Hemiarthroplasty for Hip Fracture. N Engl J Med. 2019;381(23):2199-2208. PubMed
HEALTH trial (NEJM): total hip replacement and hemiarthroplasty had similar reoperation rates at 2 years, with slightly better function and more dislocations after total hip replacement. - Ekhtiari S, Gormley J, Axelrod DE, et al. Total Hip Arthroplasty Versus Hemiarthroplasty for Displaced Femoral Neck Fracture: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. J Bone Joint Surg Am. 2020;102(18):1638-1645. PubMed
Meta-analysis: hemiarthroplasty and total hip replacement give similar revision, function and mortality up to 5 years. - Fernandez MA, Achten J, Parsons N, et al. Cemented or Uncemented Hemiarthroplasty for Intracapsular Hip Fracture. N Engl J Med. 2022;386(6):521-530. PubMed
WHiTH trial (NEJM): cemented hemiarthroplasty gave better quality of life and fewer periprosthetic fractures than uncemented. - Lewis SR, Macey R, Parker MJ, et al. Arthroplasties for hip fracture in adults. Cochrane Database Syst Rev. 2022;2(2):CD013410. PubMed
Cochrane review: cemented hemiarthroplasty likely improves overall outcome, quality of life and mortality. - Fixation using Alternative Implants for the Treatment of Hip fractures (FAITH) Investigators. Fracture fixation in the operative management of hip fractures (FAITH): an international, multicentre, randomised controlled trial. Lancet. 2017;389(10078):1519-1527. PubMed
FAITH trial (Lancet): sliding hip screw and cancellous screws had similar reoperation rates for femoral neck fractures. - Wessels JO, Bjarnesen MP, Erichsen JL, et al. Sliding hip screw vs intramedullary nail for AO/OTA31A1-A3: a systematic review and meta-analysis. Injury. 2022;53(3):1149-1159. PubMed
Meta-analysis: sliding hip screws and intramedullary nails gave similar outcomes across trochanteric fracture types. - Matre K, Vinje T, Havelin LI, et al. TRIGEN INTERTAN intramedullary nail versus sliding hip screw: a prospective, randomized multicenter study on pain, function, and complications in 684 patients with an intertrochanteric or subtrochanteric fracture and one year of follow-up. J Bone Joint Surg Am. 2013;95(3):200-8. PubMed
Randomized trial: intramedullary nails and sliding hip screws had similar pain, function and reoperation rates at 12 months. - Bretherton CP, Parker MJ. Femoral Medialization, Fixation Failures, and Functional Outcome in Trochanteric Hip Fractures Treated With Either a Sliding Hip Screw or an Intramedullary Nail From Within a Randomized Trial. J Orthop Trauma. 2016;30(12):642-646. PubMed
Randomized trial: unstable fractures treated with sliding hip screws were prone to medialization and worse function, supporting nails for unstable patterns. - Colón-Emeric C, Nordsletten L, Olson S, et al. Association between timing of zoledronic acid infusion and hip fracture healing. Osteoporos Int. 2011;22(8):2329-36. PubMed
Analysis: zoledronic acid did not impair fracture healing, even when given soon after surgery. - Hu F, Jiang C, Shen J, et al. Preoperative predictors for mortality following hip fracture surgery: a systematic review and meta-analysis. Injury. 2012;43(6):676-85. PubMed
Meta-analysis: preoperative predictors of mortality after hip fracture.
Medically reviewed by Andrew P. Dold, MD, FAOA, FAAOS, FACS, FRCSC. Last reviewed October 2026. This page is general information, not medical advice. Individual results vary.


