








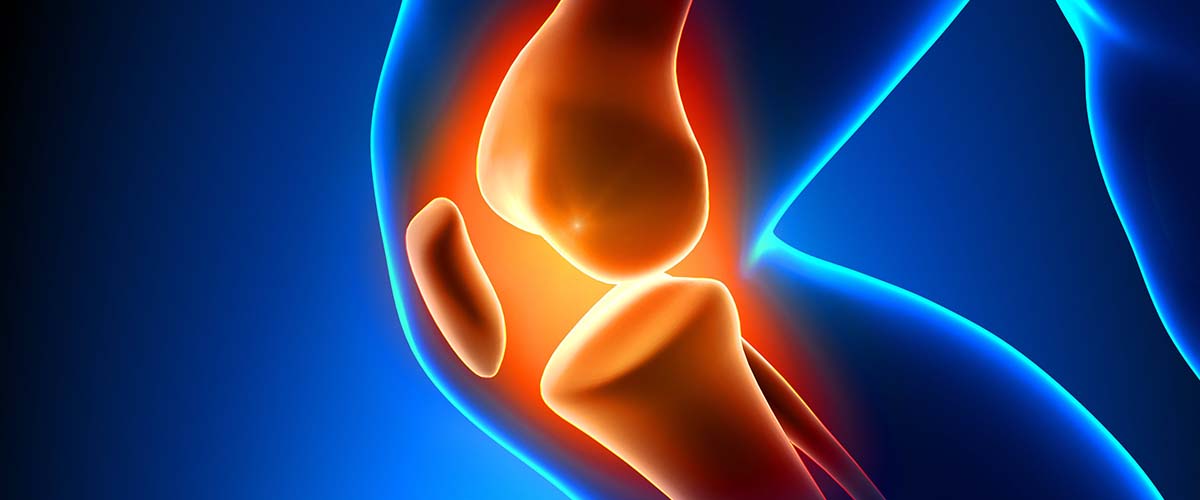
The medial collateral ligament (MCL) runs along the inner side of the knee and keeps it from buckling inward. It is the most frequently injured ligament in the knee.1 The good news is that the MCL has a strong ability to heal, and most MCL tears get better without surgery.2 Dr. Andrew Dold, a board-certified, fellowship-trained sports medicine surgeon in Frisco, Texas, treats MCL injuries from mild sprains to complex tears combined with ACL and other ligament injuries.
- Usually caused by a blow to the outside of the knee or a twisting injury
- Most MCL tears heal with a hinged brace and physical therapy
- Surgery is reserved for selected complete tears, tears that stay unstable, and some combined ligament injuries
- Many grade I–II injuries return to sport within weeks; complete tears take longer
How does the MCL tear?
MCL injuries happen with contact, such as a tackle or a blow to the outside of the knee, and without contact, such as a twisting or cutting movement.1 They are common in football, soccer, hockey, rugby and skiing. An MCL tear can occur alone or together with an ACL tear, a meniscus tear or an injury to the posteromedial corner.
MCL tear grades
| Grade | What it means |
|---|---|
| Grade I | Stretch or partial tear; the knee is tender but stable |
| Grade II | Larger partial tear; some looseness when the knee is stressed, with a firm end point |
| Grade III | Complete tear; the inner knee opens more when stressed |
Diagnosis
Dr. Dold examines the knee, testing how much the inner side opens with the knee straight and slightly bent. X-rays rule out fractures and growth-plate injuries in younger athletes. An MRI shows where the ligament tore, how severe the tear is and whether the ACL, meniscus or posteromedial corner is also injured, which changes treatment.
Treatment without surgery
Non-surgical treatment is the mainstay for MCL injuries.1 Dr. Dold’s approach usually includes:
- A hinged knee brace to protect the ligament while allowing motion
- Weight bearing as tolerated, with crutches at first if needed
- Physical therapy to restore motion, then quadriceps, hamstring and hip strength
- A gradual return to running, cutting and sport
A 2024 systematic review of nearly 2,000 patients found that immediate weight bearing was well tolerated for grade I and II injuries, although the details of rehabilitation and bracing varied widely between studies.3
When does an MCL tear need surgery?
Even complete (grade III) MCL tears often heal without surgery, so the decision to operate is individualized.2 Dr. Dold may recommend surgery when:
- The knee remains loose on the inner side after a period of bracing and rehabilitation
- The ligament is torn off the shinbone and trapped in a position where it cannot heal (a Stener-type lesion)
- The MCL tear is part of a multi-ligament injury
- The posteromedial corner is also injured, causing rotational instability
Options include repair of the torn ligament, which has shown good results for distal avulsions with good tissue,2 and reconstruction with a tendon graft. In a review of 355 repaired knees, 90% had good or near-normal stability and the failure rate was about 6%.4 Anatomic reconstruction techniques have restored stability more reliably than non-anatomic ones,5 and after MCL and posterior oblique ligament reconstruction, about 88% to 91% of patients returned to recreational sports within 6 to 12 months.6
MCL tears with an ACL tear
When the MCL and ACL are torn together, the MCL is often allowed to heal first with a brace before the ACL is reconstructed. A meta-analysis of 1,534 combined injuries found no difference in patient-reported outcomes, motion or quadriceps strength between non-surgical and surgical treatment of the MCL. If inner-knee laxity remains after rehabilitation, the MCL can be addressed at the time of ACL surgery.7
Recovery and return to sport
Recovery depends on the grade and on any other injuries. Mild injuries may return to sport within a few weeks; complete tears and surgically treated injuries take longer. Dr. Dold bases return to sport on stability, strength and sport-specific testing rather than time alone.
What the research shows
Here is what randomized trials and large studies add about MCL injuries.
Most MCL tears heal without surgery, even with an ACL tear
Randomized trials have found similar function after surgical and non-surgical treatment of MCL injuries, including complete tears. In patients with combined ACL and MCL tears, treating the MCL without surgery while reconstructing the ACL gave equally good results, and adding MCL surgery slowed early recovery of motion. In large U.S. data, more than 9 in 10 MCL injuries that occur with an ACL tear are treated without MCL surgery.
When the MCL matters for the ACL
Persistent looseness on the inner side of the knee adds stress to an ACL graft and raises the risk of graft failure. This is why the MCL is reassessed before ACL reconstruction, and why MCL surgery is considered for specific patterns, such as opening of the knee in full extension, a tibial-sided tear that cannot heal, or a posteromedial corner injury.
Repair or reconstruction
When surgery is needed, reconstruction has had lower failure and stiffness rates than repair alone in pooled studies, while augmented repair has given similar early stability in a prospective study.
Braces for prevention
The evidence on prophylactic knee braces to prevent MCL injuries in football is limited and difficult to interpret.
What patients say
Patient reviews in their own words. Individual results vary. Read more patient reviews.
Why see Dr. Dold
- Board certified by the American Board of Orthopaedic Surgery, with subspecialty certification in Sports Medicine
- Sports medicine and arthroscopy fellowship at NYU Langone / Hospital for Joint Diseases; orthopedic residency at the University of Toronto
- Fellow of the American College of Surgeons (FACS), the American Academy of Orthopaedic Surgeons (FAAOS), the American Orthopaedic Association (FAOA) and the Royal College of Surgeons of Canada (FRCSC)
- Published research on knee ligament and meniscus surgery, including The Posteromedial Corner of the Knee (JAAOS, 2017) and transtibial meniscal root repair (KSSTA, 2017)
- Team physician and surgical consultant to Rugby Canada; has cared for professional athletes from the NFL, NBA, NHL, MLS, PGA Tour and Major League Rugby
- D Magazine Best Doctors (Collin County), 2019–2026 · Rated 4.9 on Google
Frequently asked questions
Does an MCL tear need surgery?
Usually not. Most MCL tears, including many complete tears, heal with a hinged brace and physical therapy.1,2 Surgery is considered for tears that stay unstable, trapped avulsions and some multi-ligament injuries.
Can I walk with a torn MCL?
Yes, most people can walk, and weight bearing as tolerated is usually encouraged, with crutches at first if needed.3
How long does an MCL tear take to heal?
It depends on the grade. Mild sprains often recover in a few weeks, while complete tears take longer. Dr. Dold bases return to sport on stability and strength testing.
Do I need a brace for an MCL tear?
A hinged knee brace is commonly used to protect the ligament while it heals and still allow knee motion.
What if I tore my MCL and ACL together?
The MCL is often allowed to heal first with a brace, and the ACL is reconstructed afterward. If the MCL remains loose, it can be repaired or reconstructed at the same time.7
Is an MCL tear the same as a posteromedial corner injury?
No, but they often occur together. The posteromedial corner is a group of structures behind the MCL; injuries there can cause rotational instability. See posteromedial corner injuries.8
Research cited on this page
- Duffy PS, Miyamoto RG. Management of medial collateral ligament injuries in the knee: an update and review. Phys Sportsmed. 2010;38(2):48-54. PubMed
- Rechter GR, Barrera L, Daniel AV, et al. Distal Medial Collateral Ligament Avulsion Repair. Arthrosc Tech. 2025;14(6):103525. PubMed
- Svantesson J, Piussi R, Weissglas E, et al. Shedding light on the non-operative treatment of the forgotten side of the knee: rehabilitation of medial collateral ligament injuries. A systematic review. BMJ Open Sport Exerc Med. 2024;10(2):e001750. PubMed
- DeLong JM, Waterman BR. Surgical Repair of Medial Collateral Ligament and Posteromedial Corner Injuries of the Knee: A Systematic Review. Arthroscopy. 2015;31(11):2249-2255. PubMed
- DeLong JM, Waterman BR. Surgical Techniques for the Reconstruction of Medial Collateral Ligament and Posteromedial Corner Injuries of the Knee: A Systematic Review. Arthroscopy. 2015;31(11):2258-2272. PubMed
- D’Ambrosi R, Corona K, Guerra G, et al. Midterm Outcomes, Complications, and Return to Sports After Medial Collateral Ligament and Posterior Oblique Ligament Reconstruction for Medial Knee Instability: A Systematic Review. Orthop J Sports Med. 2021;9(11):23259671211056070. PubMed
- Shultz CL, Poehlein E, Morriss NJ, et al. Nonoperative Management, Repair, or Reconstruction of the Medial Collateral Ligament in Combined Anterior Cruciate and Medial Collateral Ligament Injuries: Which Is Best? A Systematic Review and Meta-analysis. Am J Sports Med. 2024;52(2):522-534. PubMed
- Dold AP, Swensen S, Strauss E, Alaia M. The Posteromedial Corner of the Knee: Anatomy, Pathology, and Management Strategies. J Am Acad Orthop Surg. 2017;25(11):752-761. PubMed
- Roberts SB, Brown OS, Beattie N, et al. Systematic review of randomised controlled trials for interventions to treat injuries to the medial ligaments of the knee. Surgeon. 2021;19(2):111-118. PubMed
A review of 8 randomized trials found surgical and non-surgical treatment of grade I–III MCL injuries gave similar function, with better quadriceps strength after non-surgical care. - Halinen J, Lindahl J, Hirvensalo E, et al. Operative and nonoperative treatments of medial collateral ligament rupture with early anterior cruciate ligament reconstruction: a prospective randomized study. Am J Sports Med. 2006;34(7):1134-40. PubMed
In a randomized trial of combined ACL and MCL injuries, non-surgical and surgical treatment of the MCL (with ACL reconstruction) gave equally good results. - Halinen J, Lindahl J, Hirvensalo E. Range of motion and quadriceps muscle power after early surgical treatment of acute combined anterior cruciate and grade-III medial collateral ligament injuries. A prospective randomized study. J Bone Joint Surg Am. 2009;91(6):1305-12. PubMed
In the same trial, repairing the MCL as well as the ACL led to slower early recovery of knee bending. - Niknam K, Goldberg D, Markes AR, et al. Concomitant Medial Collateral Ligament Injury Increases the Risk of Revision Anterior Cruciate Ligament Reconstruction. Arthroscopy. 2025;41(5):1423-1433.e4. PubMed
A database study of more than 10,000 combined ACL-MCL injuries found 93% of MCLs were treated without surgery, though surgical treatment has been increasing. - Ghiretti R, Panzavolta F, Lucidi GA, et al. Combined ACL-MCL Injuries: Anatomy, Biomechanics, and Clinical Management. Medicina (Kaunas). 2025;61(10). PubMed
A 2025 review noted that persistent medial looseness after combined ACL-MCL injury adds stress to the ACL graft and raises the risk of graft failure. - Bollier M, Smith PA. Anterior cruciate ligament and medial collateral ligament injuries. J Knee Surg. 2014;27(5):359-68. PubMed
A review recommended considering MCL surgery for opening of the joint in full extension, significant deep MCL injury or a displaced tibial-sided (Stener-type) MCL tear. - Tibor LM, Marchant MH, Taylor DC, et al. Management of medial-sided knee injuries, part 2: posteromedial corner. Am J Sports Med. 2011;39(6):1332-40. PubMed
Posteromedial corner injuries may not heal without surgery, especially with multi-ligament injuries, and should be identified before cruciate reconstruction. - Mowers C, Jackson GR, Condon JJ, et al. Medial Collateral Ligament Reconstruction and Repair Show Similar Improvement in Outcome Scores, But Repair Shows Higher Rates of Knee Stiffness and Failure: A Systematic Review. Arthroscopy. 2023;39(10):2231-2240. PubMed
A review of 18 studies found MCL repair had higher rates of stiffness and failure than reconstruction at 2 years or more. - LaPrade RF, DePhillipo NN, Dornan GJ, et al. Comparative Outcomes Occur After Superficial Medial Collateral Ligament Augmented Repair vs Reconstruction: A Prospective Multicenter Randomized Controlled Equivalence Trial. Am J Sports Med. 2022;50(4):968-976. PubMed
A prospective study found similar objective stability 1 year after augmented MCL repair and full MCL reconstruction. - Hoit G, Rubacha M, Chahal J, et al. Is There a Disadvantage to Early Physical Therapy After Multiligament Surgery for Knee Dislocation? A Pilot Randomized Clinical Trial. Clin Orthop Relat Res. 2021;479(8):1725-1736. PubMed
A randomized trial after multi-ligament surgery found no clear difference in stiffness or stability between early and delayed physical therapy. - Lundblad M, Hägglund M, Thomeé C, et al. Medial collateral ligament injuries of the knee in male professional football players: a prospective three-season study of 130 cases from the UEFA Elite Club Injury Study. Knee Surg Sports Traumatol Arthrosc. 2019;27(11):3692-3698. PubMed
In professional soccer, three-quarters of MCL injuries came from contact, and clinical grading agreed closely with MRI grading. - Kramer DE, Miller PE, Berrahou IK, et al. Collateral Ligament Knee Injuries in Pediatric and Adolescent Athletes. J Pediatr Orthop. 2020;40(2):71-77. PubMed
In children and teens, MCL injuries were 4 times more common than LCL injuries, and about a quarter occurred with kneecap dislocations. - Blecha K, Nuelle CW, Smith PA, et al. Efficacy of Prophylactic Knee Bracing in Sports. J Knee Surg. 2022;35(3):242-248. PubMed
A review found limited definitive evidence on whether prophylactic knee braces prevent MCL injuries in sports. - Albright JP, Powell JW, Smith W, et al. Medial collateral ligament knee sprains in college football. Brace wear preferences and injury risk. Am J Sports Med. 1994;22(1):2-11. PubMed
A study of college football found the effect of prophylactic braces on MCL sprains was difficult to interpret because of confounding factors.
Medically reviewed by Andrew P. Dold, MD, FAOA, FAAOS, FACS, FRCSC. Last reviewed October 2026. This page is general information, not medical advice. Individual results vary.


