








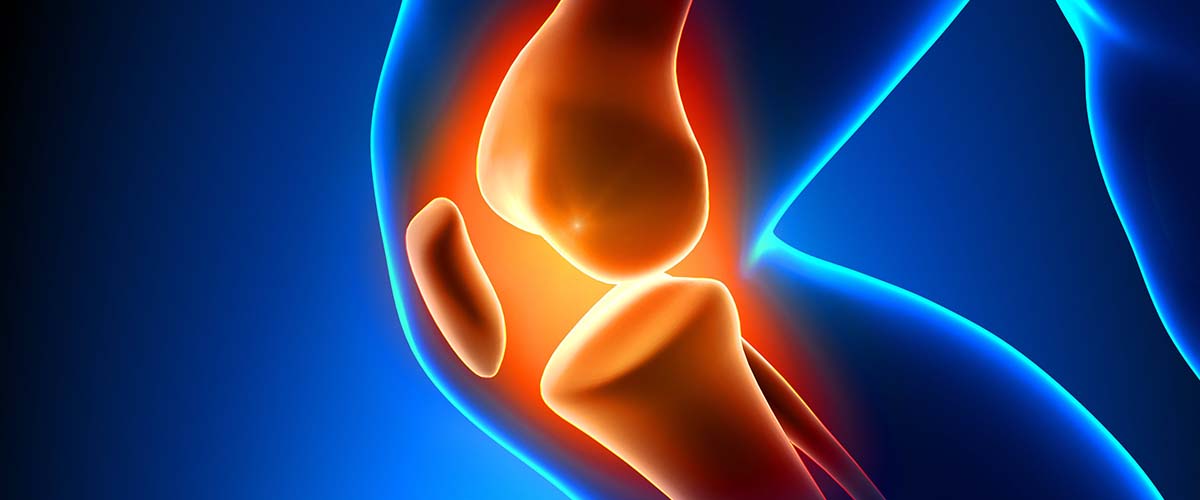
The kneecap (patella) is a key part of the knee’s extensor mechanism, which straightens the leg. A patella fracture is a common injury, caused either by a direct blow, such as a fall onto the knee or hitting a dashboard, or by a forceful pull of the thigh muscle.1 Dr. Andrew Dold, a board-certified, fellowship-trained sports medicine surgeon in Frisco, Texas, treats patella fractures with and without surgery.
- Non-displaced fractures with an intact extensor mechanism can usually be treated without surgery
- Displaced fractures, or fractures that stop you from straightening the knee, need surgical fixation
- Hardware irritation is common, and some patients later have it removed
- Thigh strength and kneecap pain can take months to improve
Symptoms
- Pain and swelling over the front of the knee after a fall or blow
- Bruising
- Difficulty or inability to straighten the knee or lift the leg with the knee straight
- A gap or step you can feel in the kneecap
Diagnosis
Dr. Dold checks whether you can straighten the knee against gravity, which shows whether the extensor mechanism is intact. X-rays show the fracture pattern and how far the pieces have separated; a CT scan helps with complex fractures.
Treatment without surgery
Non-displaced fractures with an intact extensor mechanism can be treated without surgery,1 usually with a brace or splint holding the knee straight, weight bearing as tolerated and a gradual return of motion and strengthening.
Surgery
Surgical fixation is recommended when the fracture disrupts the extensor mechanism, or when the joint surface has a step of more than 2 to 3 mm or the fragments are separated by more than about 1 to 4 mm.1 The goal is to restore a smooth joint surface and a working extensor mechanism. Fixation options include tension-band wiring with pins or screws, plates and suture-based techniques; anatomic reduction with a tension-band technique has been associated with good outcomes.1 For fractures of the lower tip of the kneecap, studies of different fixation methods report knee bending of about 120° to 135° after surgery.2
Open fractures, where the skin is broken, have more complications and need urgent cleaning and treatment.1
Recovery and what to expect
After surgery, the knee is usually protected in a brace, with motion increased gradually as the fracture heals. Physical therapy focuses on regaining motion and rebuilding quadriceps strength. Recovery takes time: in one study of patients after patella fracture surgery, many still had thigh weakness and some limitation in sport and quality of life at follow-up, and 52% had their hardware removed because it was bothersome.3 Hardware irritation is a frequent complication, and Dr. Dold can remove symptomatic hardware once the bone has healed.1
What the research shows
- Who needs surgery: fractures that are not displaced and leave the knee able to straighten (an intact extensor mechanism) are usually treated in a brace that keeps the knee straight, with protected motion. Surgery is recommended when the knee cannot be straightened against gravity or the joint surface is displaced more than about 2 mm.
- Restoring the joint surface matters: anatomic reduction of the cartilage surface is key to lowering the risk of post-traumatic arthritis. A CT scan helps plan surgery for comminuted fractures, and bone-preserving fixation is preferred over removing the kneecap.
- Fixation options: tension band wiring has been the standard, but it carries notable rates of early loss of fixation and painful hardware. Low-profile plates and suture-based constructs have shown good healing with fewer hardware problems in several studies.
- Realistic expectations: long-term studies show many patients have some residual knee symptoms, and about half needed hardware removal after traditional wiring. Removing irritating hardware improves pain and quality of life.
- Older adults: most fractures result from simple falls and are often comminuted at the lower pole. Non-surgical care can be reasonable in frail patients with limited demands.
- Children: a “sleeve” fracture can pull a cartilage sleeve off the kneecap and be missed on X-ray; a high-riding kneecap is a key clue.
Why see Dr. Dold
- Board certified by the American Board of Orthopaedic Surgery, with subspecialty certification in Sports Medicine
- Sports medicine and arthroscopy fellowship at NYU Langone / Hospital for Joint Diseases; orthopedic residency at the University of Toronto
- Fellow of the American College of Surgeons (FACS), the American Academy of Orthopaedic Surgeons (FAAOS), the American Orthopaedic Association (FAOA) and the Royal College of Surgeons of Canada (FRCSC)
- Published research on knee ligament and meniscus surgery, including The Posteromedial Corner of the Knee (JAAOS, 2017) and transtibial meniscal root repair (KSSTA, 2017)
- Team physician and surgical consultant to Rugby Canada; has cared for professional athletes from the NFL, NBA, NHL, MLS, PGA Tour and Major League Rugby
- D Magazine Best Doctors (Collin County), 2019–2026 · Rated 4.9 on Google
Frequently asked questions
Does a broken kneecap need surgery?
Not always. Non-displaced fractures with an intact ability to straighten the knee can usually be treated in a brace. Displaced fractures or those that disrupt the extensor mechanism need surgery.1
Can I walk with a fractured patella?
Often yes, in a brace locked straight, depending on the fracture and treatment. Dr. Dold will give you specific weight-bearing instructions.
Will the hardware need to come out?
Sometimes. Hardware irritation is common after patella fracture fixation, and in one study about half of patients had it removed after healing.3
How long does recovery take?
The bone usually heals over a few months, but regaining full strength can take longer. Some patients have lasting thigh weakness or kneecap pain.3
Can a patella fracture cause arthritis?
Yes. Patella fractures can lead to stiffness, weakness and arthritis behind the kneecap, which is why restoring a smooth joint surface matters.1
Think you have a fracture? See fracture care in Frisco: same-day appointments and walk-ins Monday, Wednesday and Friday, 8:30–10:30 am.
Research cited on this page
- Melvin JS, Mehta S. Patellar fractures in adults. J Am Acad Orthop Surg. 2011;19(4):198-207. PubMed
- Chang CH, Shih CA, Kuan FC, et al. Surgical treatment of inferior pole fractures of the patella: a systematic review. J Exp Orthop. 2023;10(1):58. PubMed
- LeBrun CT, Langford JR, Sagi HC. Functional outcomes after operatively treated patella fractures. J Orthop Trauma. 2012;26(7):422-426. PubMed
- Schuett DJ, Hake ME, Mauffrey C, et al. Current Treatment Strategies for Patella Fractures. Orthopedics. 2015;38(6):377-84. PubMed
Review: surgery for extensor disruption or significant step-off or displacement; tension band fixation is most common but has drawbacks. - Henrichsen JL, Wilhem SK, Siljander MP, et al. Treatment of Patella Fractures. Orthopedics. 2018;41(6):e747-e755. PubMed
Review: tension band constructs are most common, with cerclage for comminuted fractures. - Steinmetz S, Brügger A, Chauveau J, et al. Practical guidelines for the treatment of patellar fractures in adults. Swiss Med Wkly. 2020;150:w20165. PubMed
Practical guideline: anatomic reconstruction of the joint surface is essential to prevent post-traumatic arthritis; CT helps classify fractures. - Howatt J, Liew AS, Wilkin G. Patellar Fractures: Anatomy, Mechanics, and Surgical Management. J Bone Joint Surg Am. 2021;103(23):2237-2246. PubMed
Review: bone-preserving procedures are recommended and patellectomy should be avoided. - Sayum Filho J, Lenza M, Teixeira de Carvalho R, et al. Interventions for treating fractures of the patella in adults. Cochrane Database Syst Rev. 2015(2):CD009651. PubMed
Cochrane review: very limited randomized evidence on surgical techniques for patella fractures. - Pritchett JW. Nonoperative treatment of widely displaced patella fractures. Am J Knee Surg. 1997;10(3):145-7; discussion 147-8. PubMed
Study: non-operative treatment of displaced fractures in medically ill older patients gave acceptable function. - Sim JA, Joo YB, Choi W, et al. Patellar fractures in elderly patients: a multicenter computed tomography-based analysis. Arch Orthop Trauma Surg. 2021;141(9):1439-1445. PubMed
Study in older adults: most fractures were low-energy, often with lower-pole comminution; complications and reoperations were common. - Greenberg A, Kadar A, Drexler M, et al. Functional outcomes after removal of hardware in patellar fracture: are we helping our patients?. Arch Orthop Trauma Surg. 2018;138(3):325-330. PubMed
Study: removing symptomatic hardware improved quality of life and pain. - Taylor BC, Mehta S, Castaneda J, et al. Plating of patella fractures: techniques and outcomes. J Orthop Trauma. 2014;28(9):e231-5. PubMed
Review: tension band fixation remains standard but carries significant complication and symptomatic implant rates; plating is an alternative. - Smith ST, Cramer KE, Karges DE, et al. Early complications in the operative treatment of patella fractures. J Orthop Trauma. 1997;11(3):183-7. PubMed
Study: 22% of tension band fixations displaced early, related to technical errors or non-compliance. - Moore TB, Sampathi BR, Zamorano DP, et al. Fixed angle plate fixation of comminuted patellar fractures. Injury. 2018;49(6):1203-1207. PubMed
Study: fixed-angle plating of comminuted fractures gave good to excellent function with low complication and hardware-removal rates. - Shymon SJ, Jansson H, Schneiderman BA, et al. Functional Outcomes of Patella Fractures Treated With Anterior Plate Osteosynthesis at One Year. J Orthop Trauma. 2021;35(1):e1-e6. PubMed
Study: plate fixation had no nonunions or fixation failures and only 5.5% needed implant removal. - Meng D, Xu P, Shen D, et al. A clinical comparison study of three different methods for treatment of transverse patellar fractures. J Orthop Sci. 2019;24(1):142-146. PubMed
Comparative study: plating had the lowest risk of symptomatic implant complications. - Camarda L, Morello S, Balistreri F, et al. Non-metallic implant for patellar fracture fixation: A systematic review. Injury. 2016;47(8):1613-7. PubMed
Systematic review: non-metallic (suture) fixation gives good outcomes and reduces hardware removal. - Camarda L, La Gattuta A, Butera M, et al. FiberWire tension band for patellar fractures. J Orthop Traumatol. 2016;17(1):75-80. PubMed
Study: suture tension bands gave satisfactory results with few complications and reoperations. - Mao N, Liu D, Ni H, et al. Comparison of the cable pin system with conventional open surgery for transverse patella fractures. Clin Orthop Relat Res. 2013;471(7):2361-6. PubMed
Randomized trial: a minimally invasive cable pin technique reduced early pain and improved early motion compared with open K-wire fixation. - Boeckxstaens A, Hoekstra H, Depypere M, et al. Fracture-related infection of the patella: Treatment options and outcome. Injury. 2022;53(6):1880-1886. PubMed
Study: fracture-related infection occurred in 9.3% after patella fracture surgery. - Larsen P, Vedel JO, Vistrup S, et al. Long-Lasting Hyperalgesia Is Common in Patients Following Patella Fractures. Pain Med. 2018;19(3):429-437. PubMed
Study: long-lasting local pain sensitivity after patella fracture is common. - Gao GX, Mahadev A, Lee EH. Sleeve fracture of the patella in children. J Orthop Surg (Hong Kong). 2008;16(1):43-6. PubMed
Pediatric study: patellar sleeve fractures can be missed; displaced injuries need surgical repair. - Hunt DM, Somashekar N. A review of sleeve fractures of the patella in children. Knee. 2005;12(1):3-7. PubMed
Review: sleeve fractures in children may show only a high-riding patella on X-ray; ultrasound helps.
Medically reviewed by Andrew P. Dold, MD, FAOA, FAAOS, FACS, FRCSC. Last reviewed October 2026. This page is general information, not medical advice. Individual results vary.

